Summary
This document discusses a new nasal spray designed to safely and effectively capture and neutralize a wide range of respiratory pathogens, potentially preventing infections without the use of drugs.
Key points
- PCANS is a drug-free nasal spray designed to prevent respiratory infections.
- It captures and neutralizes pathogens in the nasal cavity.
- Demonstrated over 99.99% reduction in pathogen load in studies.
- Safe for daily use and shows prolonged nasal retention.
- Effective against a broad spectrum of viruses and bacteria.
- Potential to complement existing vaccines and enhance public health.
A Drug-Free Pathogen Capture and Neutralizing Nasal Spray to
- Prevent Emerging Respiratory Infections
3
- John Joseph1,2,3#, Helna Mary Baby1,2,#, Joselyn Rojas Quintero3,4#, Devin Kenney5,6, Yohannes A Mebratu3,4,
- Eshant Bhatia7, Purna Shah2, Kabir Swain2, Shahdeep Kaur1,2,3, Xiang-Ling Li1,2, John Mwangi1,2, Olivia
- Snapper1,2, Remya Nair3, Eli Agus1,2, Sruthi Ranganathan1,2, Julian Kage1,2, Jingjing Gao1,2,3, James N Luo3,8,
- Anthony Yu1,2,3, Florian Douam5,6 , Yohannes Tesfaigzi3,4,, Jeffrey M Karp1,2, 3, 9, 10,11,, Nitin Joshi1,2,3,*
- 1Center for Accelerated Medical Innovation, Department of Anesthesiology, Perioperative and Pain Medicine,
- Brigham and Women’s Hospital, Boston, MA 02115, USA
- 2Center for Nanomedicine, Department of Anesthesiology, Perioperative and Pain Medicine, Brigham and
- Women’s Hospital, Boston, MA 02115, USA
- 3Harvard Medical School, Boston, MA 02115, USA
- 4Division of Pulmonology, Brigham and Women’s Hospital, Boston, MA 02115, USA
- 5National Emerging Infectious Diseases Laboratories, Boston University, Boston, MA 02118, USA
- 6Department of Microbiology, Boston University, Chobanian & Avedisian School of Medicine, Boston, MA, USA
- 7Indian Institute of Technology, Mumbai, India
- 8Department of Surgery, Brigham and Women’s Hospital, Boston, MA 02115, USA
- 9Harvard–Massachusetts Institute of Technology Division of Health Sciences and Technology, Massachusetts
- Institute of Technology, Cambridge, MA 02139, USA
- 10Broad Institute, Cambridge, MA 02142, USA.
- 11Harvard Stem Cell Institute, Cambridge, MA 02138, USA
- Corresponding authors. Email: ytesfaigzi@bwh.harvard.edu, jmkarp@bwh.harvard.edu;
- njoshi@bwh.harvard.edu
- #These authors contributed equally to this work.
25
26
27
Abstract
- Respiratory infections pose a global health crisis. Vaccines are pathogen specific, and new vaccines are
- needed for mutants and emerging pathogens. Here, we report a “drug free” prophylactic platform - a “Pathogen
- Capture and Neutralizing Spray” (PCANS) that acts via a multi-pronged approach to prevent a broad spectrum
- of respiratory infections. PCANS forms a protective coating in the nasal cavity that enhances the capture of large
- respiratory droplets. The coating acts as a physical barrier against a broad spectrum of viruses and bacteria,
- and rapidly neutralizes them, reducing the pathogen load by >99.99%. In mice, PCANS showed nasal retention
- for at least 8 h and was safe for daily administration. A single prophylactic dose of PCANS protected mice against
- supra-lethal dosages of a mouse-adapted H1N1 Influenza virus (PR8), reduced lung viral titer by >99.99%,
- improved survival, and suppressed pathological manifestations. Together, our data suggest PCANS as a
- promising daily-use prophylactic approach against current and emerging respiratory infections.
Introduction
Respiratory infections result in significant morbidity and mortality worldwide(1). The past few decades have
witnessed numerous outbreaks, often leading to epidemics or unanticipated pandemics such as COVID-19.
Although vaccines are available against Influenza A virus (IAV), severe acute respiratory syndrome coronavirus
2 (SARS-CoV-2), respiratory syncytial virus (RSV) and Streptococcus pneumoniae, the emergence of mutants
often reduces the efficacy of vaccines(2). Additionally, there are several pathogens, including adenovirus,
Klebsiella pneumoniae, Staphylococcus aureus, and E.Coli, which can cause severe respiratory diseases, but
do not have clinically available vaccines, as of now. In the face of an unforeseen pandemic, the timeline for
developing vaccines targeting a pathogen can range from 1 to 10 years, contingent upon the specific nature of
the pathogen(3, 4). The rapid creation of efficacious COVID-19 vaccines stands as an unparalleled scientific
achievement. However, it took several months for the vaccine to become available, during which numerous
hospitalizations and deaths were reported (5). Additionally, multiple obstacles, such as production complexities,
vaccine nationalism, and the emergence of novel variants, collectively posed major challenges around the world.
Another concern pertaining to vaccines is their partial mitigation of the pathogen burden(6, 7), which implies that
vaccinated people can still contract and disseminate the infection, albeit at a reduced rate compared to those
who are unvaccinated. In addition, a large percentage of the population did not consent to vaccination for various
reasons. Thus, there is a critical need to develop a pre-exposure prophylactic approach that can be easily and
rapidly employed either independently or in tandem with vaccines, serving as the primary safeguard against
current and emerging respiratory pathogens. Such an approach should efficiently reduce pathogen load, and be
radically simple to scale up and manufacture to ensure widespread global adoption.
Transmission of most respiratory pathogens predominantly occurs through inhalation of contaminated
respiratory droplets and their subsequent deposition in the nasal cavity, which has an entry checkpoint(8). For
instance, SARS-CoV-2 virus binds to the angiotensin-converting enzyme 2 (ACE2) located in nasal epithelial
cells via its receptor-binding domain (RBD). The nasal cavity is a primary target for SARS-CoV-2 infection due
to high expression of ACE2(9–11), which decreases towards the lower respiratory tract(12). The infection
spreads to the deeper airways via virus-laden extracellular vesicles secreted by infected cells in the nasal
cavity(13). Similarly, bacteria, including Streptococcus pneumoniae and Staphylococcus aureus adhere to nasal
mucin via a specific adhesin receptor(14, 15). Considering the vulnerability of nasal cavity and its critical role in
the transmission of respiratory pathogens, chemoprophylactic nasal sprays have been developed to offer pre-
exposure prophylaxis against respiratory infections. This approach utilizes chemical agents, including small
molecule drugs, antiseptics, or nitric oxide, to deactivate the pathogen in the nasal cavity or a polymer that acts
as a physical barrier to prevent pathogen entry through the nasal lining(16, 17). Although multiple pre-exposure
chemoprophylactic approaches have been previously developed(18–20), they have resulted in suboptimal
efficacy with only 20-60% protection achieved in pre-clinical and clinical studies(21–23). We contend that the
sub-optimal clinical efficacy of previous chemoprophylactic nasal sprays can be attributed, at least in part, to
their dependence on a single mode of action, which usually entails either pathogen neutralization or the creation
of a physical barrier to hinder pathogen entry through the nasal lining. Furthermore, since pathogens gain access
to the nasal cavity through large respiratory droplets(24), an optimal prophylactic strategy should also prioritize
the effective capture of these droplets laden with pathogens. This necessitates preventing them from bouncing
off, a factor that has not been addressed in prior approaches. Previous approaches also consist of a single active
ingredient that targets a limited type/class of pathogen(21, 25–28), which could potentially undermine their
effectiveness when confronted with newly emerging pathogens. Finally, many chemoprophylactic nasal sprays
are unsuitable for repeated/daily application due to toxicity concerns(29, 30).
Herein, we report a Pathogen Capture and Neutralizing Spray (PCANS) that overcomes the aforementioned
limitations of previously developed chemoprophylactic nasal sprays, thereby achieving superior efficacy. PCANS
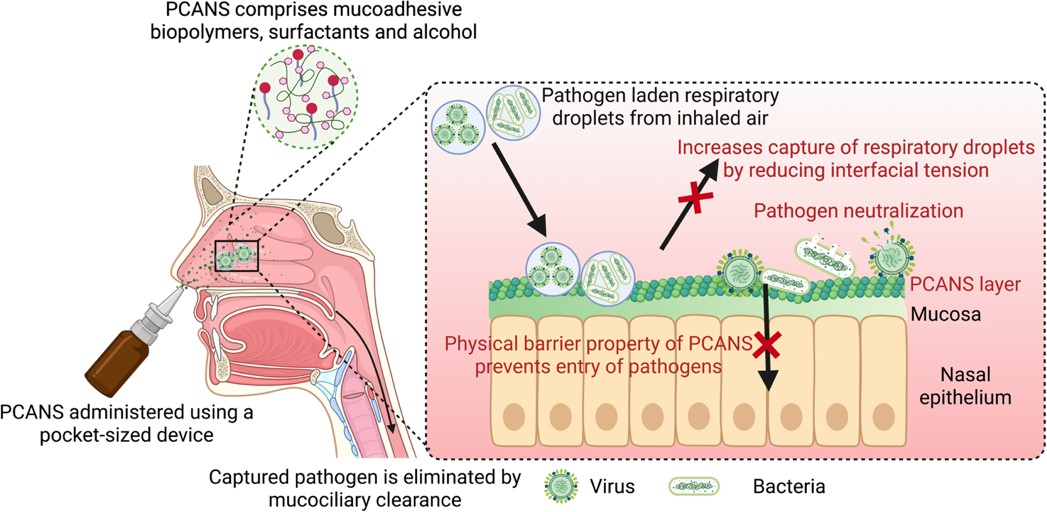
has been engineered to act via a multi-pronged approach that involves three key steps (Fig. 1). First, PCANS
enhances the capture of pathogen-laden respiratory droplets from inspired air by preventing them from bouncing
off the nasal lining. To achieve this, we adopted a biomimetic approach that involves reducing the interfacial 00 tension of the nasal lining, similar to pulmonary surfactants in alveoli. Second, PCANS forms a physical barrier 01 over nasal mucosa to intercept invasion/colonization of different pathogens. Last, PCANS consists of multiple 02 “non-drug” agents that rapidly neutralize a wide range of pathogens. We define 'neutralization' as a process that 03 impedes pathogen entry into host cells by either destabilizing the pathogen cell membrane or blocking the 04 receptor-mediated binding/fusion of the pathogen through chemical interactions. To ensure safety during daily 05 or repeated use, PCANS was meticulously designed as a "drug-free" formulation, incorporating biopolymers,
the highest sprayable concentration before and after the addition of simulated nasal fluid (SNF). SNF was added
to mimic the physiological environment in the nasal cavity. Mechanical strength was measured using a rotational
rheometer and quantified as storage modulus (G’), which represents the amount of structure present in a
material(33). In the presence of SNF, gellan showed the highest G’ as compared to other biopolymers (Fig. 2g),
indicating its superior mechanical strength. Gellan showed a 100-fold increase in its G’ in the presence of SNF
(Fig. 2g), which is consistent with its ability to undergo in situ gelation under physiological conditions. Mono and
divalent cations present in the SNF complex with glucuronic monomeric units of gellan to form a crosslinked
hydrogel(34). Compared to gellan, other biopolymers showed minimal or no increase in their storage modulus,
suggesting poor in situ gelation. To investigate physical barrier property of biopolymers, a trans-membrane assay
was devised (Fig. S1), which involved evaluating the transport of IAV through an SNF-coated cell strainer (pore
size ~70 µm) or a cell strainer coated with simulated mucus/SNF mixture or a biopolymer/SNF mixture. After 4
h, the viral titer in the chamber below the strainer was quantified by performing a plaque assay in Madin-Darby
canine kidney (MDCK) host cells. Consistent with its excellent mechanical strength, Gellan/SNF reduced the
transport of IAV particles by >4-log fold (99.99%) as compared to only SNF-coated or mucus/SNF-coated
strainers (Fig. 2h). Xanthan/SNF, CMC/SNF and HPMC/SNF also significantly reduced the IAV transport, but
not as efficiently as gellan/SNF. Interestingly, despite significantly lower mechanical strength of pectin/SNF as
compared to gellan/SNF, it intercepted the IAV transport with similar efficiency as gellan/SNF. Carrageenan, a
biopolymer used in previously reported and commercially available chemoprophylactic nasal sprays(35), was
used as a control and did not reduce IAV transport in the presence of SNF.
Reduction in the transport of IAV particles by anionic biopolymers could be a result of their physical barrier
property and/or electrostatic interactions between their negatively charged polymeric chains and the positively
charged capsid of IAV. To decouple the effects of physical barrier property and electrostatic interactions, we
studied the transport of a low molecular weight anionic dye, rhodamine B isothiocyanate, that would abate
electrostatic interactions with the anionic biopolymers. Gellan/SNF resulted in 100% reduction in the transport of
the dye, confirming excellent physical barrier property (Fig. 2i). Other biopolymers did not reduce the transport
of the dye, indicating their poor physical barrier property. This also indicates that the reduction in IAV transport
by pectin was primarily mediated via electrostatic interaction of pectin’s chains with the virus capsid. Interestingly,
gellan/SNF reduced the transport of rhodamine B dye in a concentration-dependent manner (Fig. 2j), which was
consistent with the concentration-dependent increase in the mechanical strength (G’) of gellan in the presence
of SNF (Fig. S2). A 0.2% w/v concentration of gellan also reduced the transport of E.coli bacteria by >8-log fold
(100%) (Fig. S3), suggesting it’s broad spectrum physical barrier property to limit the transport of both viruses
and bacteria. Mucus, on the other hand, only showed a 1-log fold (90%) reduction. To conclude, gellan at a
concentration of 0.2% w/v and above impeded the transport of rhodamine B dye, E. coli, and IAV by 100%.
To ensure maximum coverage of the nasal cavity, we evaluated the spray characteristics of gellan at a
concentration of 0.2% w/v or higher with a hydraulic spray nozzle. Plume geometry and spray coverage were
measured with a high-speed image acquisition system. Increasing gellan concentration resulted in a significant
reduction in the angle of emitted plume of the spray (defined as ‘plume angle’) and coverage area (Fig. S4a-d).
Next, we evaluated the retention ability of gellan and other biopolymers at the mucosal tissue upon spraying.
Mucosal retention was measured as the drip length, defined as the distance traversed in 4 h by the biopolymer
from the point of deposition on sheep’s intestinal mucosa placed vertically. To visualize dripping, biopolymers
were mixed with a brilliant green dye. The percentage drip length of each biopolymer was calculated with respect
to the drip length of the free dye. Gellan demonstrated excellent mucosal retention with zero drip length (Fig. 2k
and Fig. S5). Other biopolymers, including carrageenan, which was used as a control showed >95% drip length,
indicating poor mucosal retention. Gellan’s superior mucosal retention is attributed to its ability to strongly
entangle with mucin glycoprotein in the mucosal tissue during the sol-gel transition(36).
Identifying agents for neutralizing a broad-spectrum of respiratory pathogens: To impart PCANS a
broad-spectrum pathogen neutralization ability, we screened agents from three different classes of compounds,
including biopolymers, surfactants, and alcohols. These compounds were selected based on their previously
reported ability to neutralize different types of pathogens(37–39). To maximize safety and translatability of
PCANS, we only selected agents that are listed in the IID or GRAS list of the FDA and are present as excipients
in commercially available nasal/topical formulations (Fig. 3a). We first evaluated the neutralization ability of these
agents against viruses. Neutralization was studied in vitro by incubating each agent individually with either IAV
or SARS-CoV-2 for 10 or 60 min, followed by 1-min centrifugation and subsequent infection of target cells with
the supernatant evaluated using plaque forming or focus-forming assay. We chose IAV and SARS-CoV-2 due
to their high prevalence worldwide as respiratory viruses and also due to a difference in their capsid proteins and
the envelope transmembrane protein. BKC fits into the pentameric ion channels at the N terminus of the
transmembrane domain through interaction with Thr11 and potentially blocks the influx/efflux of ions (Fig. 3n).
To determine the role of electrostatic interaction in pectin- and BKC-mediated neutralization of IAV and SARS-
CoV-2, respectively, we performed a neutralization assay by pre-treating pectin and BKC with counter ions to
offset the charge. As anticipated, anionic pectin in the presence of positively charged polyethyleneimine lost its
neutralization activity and failed to show a significant reduction in the viral load compared to PBS (Fig. 3f).
Likewise, the pretreatment of BKC with negatively charged bovine serum albumin diminished the ability of BKC
to reduce the SARS-CoV-2 titer in the host cells (Fig. 3k).
Next, we investigated whether ionic interactions between anionic gellan or pectin with cationic BKC, when
present together in a formulation, would impact the neutralization ability of pectin or BKC. Notably, the
neutralization efficiency of pectin (0.75% w/v) against IAV remained conserved even with a dose-dependent
increase in BKC up to a concentration of 0.1% w/v (Fig. 3o). Neutralization efficiency of BKC (0.01% w/v) against
SARS-CoV-2 was not impacted by gellan or pectin at 0.2% w/v or 0.75% w/v concentrations, respectively, but
reduced at higher concentrations (Fig. 3p,q). These results further underscore that the concentration of each
agent is critical for efficient neutralization.
Finally, we also screened surfactants and alcohols to assess their neutralization ability against bacteria,
including E. coli and Klebsiella pneumoniae (K. pneumoniae). Neutralization was determined by measuring the
bactericidal activity. Each agent was individually incubated with either E. coli or K. pneumoniae for 30 or 60 min,
followed by 1-min centrifugation, and then evaluating the bacterial load in the supernatant using a colony-forming
assay. BKC was more effective than non-ionic surfactants, resulting in a 4-log fold (99.99%) and 7-log fold
(99.99%) reduction in colony-forming units (CFU) of E. coli and Klebsiella pneumoniae, respectively, with an
incubation time of 30 min (Fig. 3r, t). Alcohols had a negligible bactericidal effect over the exposure periods of
30 or 60 min (Fig. 3s,u). Altogether, our data on physical barrier property, spray pattern, mucosal retention, and
neutralization indicate gellan, pectin, and BKC as the three critical components to formulate PCANS. However,
we also incorporated phenethyl alcohol (PEA), as it is commonly added as a stabilizer to nasal formulations to
prevent the growth of gram-negative bacteria and fungi (44) and ensure long shelf life.
Utilizing surfactants to promote the capture of respiratory droplets: Pulmonary surfactant layers the
alveolar epithelium to enhance wettability and trap airborne particles(46). We adopted this biomimetic approach
to capture pathogen-laden respiratory droplets in the nasal cavity. Specifically, we identified surfactants to reduce
interfacial tension of PCANS and reduce the bounce off/escape of respiratory droplets. We evaluated surfactants
listed in the IID list, including Tween-20, Tween-80, and BKC. Screening was performed using a twin impinger,
which is a glass apparatus that can be used to assess the deposition of aerosolized particles in different regions
of the respiratory tract (47, 48)(Fig. 4a). Simulated mucus or a biopolymer mixture of gellan and pectin without
or with different concentrations of surfactants was sprayed into the SNF-coated oropharyngeal region of the
impinger (Fig. 4a). Droplets with mass medial aerodynamic diameter >5 µm and laden with rhodamine B-loaded
liposomes (size ~400 nm) were generated using a jet nebulizer to mimic pathogen-laden large respiratory
droplets. Droplet capture was determined by quantifying the fluorescence intensity of rhodamine B in the
biopolymer/surfactant mixture or the mucus layer. Biopolymer mixture without any surfactant showed similar
fluorescence intensity as mucus (Fig. 4b). Combining the biopolymer mixture with Tween-80 or Tween-20 at a
concentration higher than 0.005% w/v or with BKC at a concentration higher than 0.01% w/v resulted in a
significant increase in the fluorescence intensity as compared to mucus or only biopolymer mixture, suggesting
increased capture of droplets due to surfactants. Compared to Tween-20, BKC and Tween-80 resulted in a
significantly higher fold increase in the fluorescence intensity when added to the biopolymer mixture at a
concentration of 0.05% w/v or higher (Fig. 4b). At 0.05% w/v concentration, both BKC and Tween-80 containing
biopolymer mixtures showed similar fluorescence intensity, which was 4-fold higher than the fluorescence
intensity of mucus or biopolymer mixture without a surfactant. Since 0.01 % w/v is the most commonly used
concentration of BKC in commercially available nasal formulations(49, 50), and also showed excellent
neutralization activity against SARS-CoV-2, we decided to use this concentration, even though BKC didn’t
increase the capture of respiratory droplets at this concentration. To impart respiratory droplet-capturing ability,
we decided to proceed with Tween-80 and determined its safe concentration that would not compromise the
permeability or metabolic activity of nasal epithelium. To that end, we performed an in vitro assay evaluating the
transepithelial electrical resistance (TEER) across the human nasal epithelial cell (RPMI-2650)-based monolayer
upon treatment with different concentrations of tween-80. A transient dip of less than 15% in TEER was observed
in the monolayer immediately after the addition of Tween-80, irrespective of the concentrations evaluated in this
study. However, the TEER reversed rapidly to the original value in less than 1 h after replacing tween-80-
containing medium with fresh medium (Fig. 4c). The drop in the TEER for Tween-80 was significantly less
and droplet size distribution (Fig. 5o-r and Fig. S10). PCANS also displayed no changes in its neuralization
activity over 60 days, resulting in >99.99% reduction in Influenza A and SARS-CoV-2 viral loads in the host cells
upon 10 min of incubation (Fig. 5s). Collectively, these data confirm the shelf-stability of PCANS.
**PCANS exhibits prophylactic activity **in vivo: Next, in a proof-of-concept study, we investigated the
prophylactic efficacy of PCANS against respiratory infection in vivo. PR8, a mouse-adapted strain of H1N1
Influenza virus, was used to induce infection. PR8 is a highly virulent strain that induces severe respiratory
infection in mice(55), and can be lethal at a dose of 10 PFU(56). In vitro assay revealed excellent potency of
PCANS to neutralize 106 PFU of PR8 within 10 min of incubation, resulting in >5-log fold (>99.99%) reduction of
the viral load in host cells (Fig. S11). To demonstrate efficacy in vivo, PCANS or PBS (10 µl) was administered
prophylactically to both the nostrils of healthy mice on day 0 (Fig. 6a). Fifteen minutes later, animals were
challenged intranasally with PR8 (250 PFU), a dose that been previously used by other groups(57, 58).
Remarkably, all mice in the PCANS-treated group survived for at least 10 days after the infection, whereas the
PBS-treated group showed 100% lethality by day 8 (Fig. 6b). Over 10 days, no discernible change was observed
in the body weight of the PCANS-treated animals, while significant weight loss was observed for PBS-treated
ones after 3 days post-infection (Fig. 6c). PCANS also curtailed the lung viral titer to undetectable levels on days
2 and 4 post-infection, resulting in >5-log fold (>99.99 %) reduction compared to PBS-treated mice (Fig. 6d-e).
Compared to healthy mice, mice infected with PR8 and treated with PBS showed significant differences in the
levels of inflammatory cells, including leukocytes, neutrophils, lymphocytes, and macrophages in
bronchoalveolar lavage (BAL) fluid (Fig. 6f-i). Prophylactic treatment of mice with PCANS restored the levels of
inflammatory cells in BALF to normal. Additionally, cytokine profile from lung homogenate showed a significant
reduction of IL-6 and TNF-a levels in PCANS-treated mice, as compared to the PBS-treated group (Fig. 6j-l). No
reduction was, however, observed in the levels of IL-1�. Histological examination of lung sections revealed a
substantial reduction in leukocyte infiltrates in PCANS-treated mice, as compared to the PBS-treated group,
which showed an abundant presence of bronchial and alveolar infiltrates (Fig. 6m). Overall, compared to PBS-
treated mice, we observed a significant reduction in pulmonary inflammation score for PCANS-treated group
(Fig. S12). An escalated dose challenge was performed to determine the potency of PCANS to neutralize a
higher viral load of PR8 (500 PFU). Compared to the PBS-treated group, prophylactic treatment with PCANS
significantly improved survival and body weight and reduced lung viral titer on days 2 and 4 post-infection (Fig.
S13). These data clearly indicate the potential of nasally administered PCANS to protect against respiratory
infection in mice.
Discussion
We report a chemoprophylactic nasal spray, PCANS – a radically simple and scalable pre-exposure
prophylaxis approach to offer protection against current and emerging respiratory pathogens. PCANS acts via a
multi-pronged approach that involves enhancing the capture of pathogen-laden large respiratory droplets from
inhaled air, acting as a physical barrier to prevent the transport of respiratory pathogens through nasal lining,
and rapid neutralization of a broad spectrum of respiratory pathogens. Unlike vaccines, which are pathogen-
specific and exhibit reduced efficacy as the pathogen mutates(59), PCANS has broad spectrum activity, with
potential to target both current and emerging respiratory pathogens. In a proof-of-concept study performed in
mice, a single intranasal dose of PCANS was effective as early as 15 min after administration and provided
protection against supra-lethal dosages of a highly virulent mouse-adapted strain of H1N1 Influenza virus (PR8),
efficiently reducing the lung viral titer by over 80-99.99%. This implies potential use of PCANS as an additional
layer of protection in conjunction with vaccines to minimize pathogen load, which is otherwise difficult to achieve
with vaccines alone. For example, in a clinical study, participants vaccinated with BNT162b2 and mRNA-1273
had only 40 percent less detectable virus compared to those who were unvaccinated when infected(60).
PCANS embodies multiple advantages over previously developed chemoprophylactic nasal sprays. First,
PCANS exhibits neutralization activity against multiple pathogens, including both bacteria and viruses
(enveloped and non-enveloped). Most of the previously developed nasal sprays, on the contrary, consist of a
single active ingredient that targets a limited type/class of pathogen. For example, nasal sprays containing iota
and kappa carrageenan (Carragelose®/Dual Defence®), xylitol (Xlear Nasal Spray®), or ethyl lauroyl arginine
hydrochloride (COVIXYL-V®) have reported activity only against IAV and SARS-CoV-2(18, 25–28). Second,
compared to other previously developed chemoprophylactic nasal sprays that require 0.5-2 h for pathogen
neutralization(25, 28), PCANS can rapidly neutralize both bacteria and viruses within 10-30 min, and also
showed higher effectiveness. For instance, PCANS achieved a 5-log fold reduction in the viral load of SARS-
CoV-2 within 10 min, while a xylitol-based nasal spray reduced viral titer by 2.5 log fold in 25 min(61). In this
study, iota + kappa carrageenan, the key component of a commercially available nasal spray-Dual Defence,
8 h in the mouse nasal cavity and provides protection for several hours. To the best of our knowledge, this is the
longest nasal residence time that has been reported for chemoprophylactic nasal sprays in mice. Such a long
nasal residence time would potentially minimize dosage frequency in humans, offering an advantage over
previously developed chemoprophylactic approaches, including SaNOtize® that require 3-6 doses per day due
to short half-life of NO(64, 65). Mechanistic studies performed in mice demonstrated that the prolonged nasal
residence time of PCANS is due to the presence of tween-80. Although different surfactants, including tween-80
have previously been shown to slow mucociliary clearance by reducing the cilia beat frequency(52), further study
is warranted in the future to comprehend the mechanism of tween-80-induced delayed nasal clearance of
PCANS. However, our study confirmed that daily administration of PCANS in mice is safe, with no evidence of
inflammation or any other nasal toxicity observed after a repeated dosing for at least 14 days.
Our study has several strengths. First, the components constituting PCANS were identified via rigorous in
vitro and in vivo screenings of multiple excipients from the IID and GRAS list of the FDA, and their different
concentrations and combinations. These extensive screening experiments were aimed to optimize the key
parameters, including sprayability, mucoadhesiveness, capture of respiratory droplets, physical barrier property,
broad spectrum pathogen neutralization activity, and nasal residence time. Second, to evaluate the respiratory
droplet capturing ability of PCANS, we used a 3D- model of human nasal cavity (Koken cast), which is based on
a female cadaver and has been previously used for in vitro evaluation of nasal drug delivery, as it replicates all
the anatomical intricacies of human nasal cavity(51). Third, physical barrier property of different biopolymers was
evaluated by two complementary techniques – quantification of viral transport using a plaque-forming assay and
quantification of the transport of small molecule dye using fluorescence spectroscopy. Fourth, we demonstrated
broad spectrum physical barrier property and neutralization ability of PCANS in five different pathogens – three
enveloped viruses (IAV, SARS-CoV-2, RSV), one non-enveloped virus (adenovirus), and two bacteria (E. coli
and K. pneumoniae). To our understanding, this is the first report demonstrating such a broad-spectrum activity
of a chemoprophylactic nasal spray. Lastly, to demonstrate prophylactic efficacy of PCANS in vivo, we used a
highly virulent mouse-adapted strain of H1N1 Influenza virus (PR8) that induces severe respiratory infections in
mice(55). Prophylactic efficacy of PCANS was demonstrated against three different dosages of the virus, which
were 10-50 times higher than the previously established lethal dose for PR8 in mice(56). Due to its prolonged
nasal residence time, PCANS was effective for several hours after nasal administration.
In conclusion, PCANS presents a promising chemoprophylactic approach against respiratory infections.
Besides its potential to act as a first line of defense against respiratory pathogens and emerging variants for
which there are no vaccines available, our approach could also be used as an added layer of protection with
existing vaccines**.** Given its broad-spectrum prophylactic activity and excellent shelf stability, we anticipate
PCANS holds the potential for global distribution, especially in countries with low vaccination rates against
respiratory pathogens. Alongside, the benefits of PCANS can also be extended to immunocompromised patients,
high-risk individuals with co-morbidities, and vaccine-hesitant populations. Its pocket-sized spray format allows
for easy portability, making it convenient to carry during social gatherings and travel. With these significant
benefits, we believe PCANS will experience rapid widespread adoption, enhancing the accessibility of respiratory
infection prevention. By enabling people to breathe clean and minimizing the transmission of respiratory
infections, PCANS can play a pivotal role in safeguarding public health worldwide.
Methods
Preparation of biopolymer solutions and PCANS. Biopolymer solutions were prepared by the addition of
the biopolymer (0.2 to 2% w/v) to ultrapure deionized sterile water (Invitrogen). The solution was then mixed to
attain a homogenous mixture with slight heating at 60oC. Biopolymers including gellan (Gelzan), pectin,
carboxymethylcellulose (CMC), hydroxypropyl methylcellulose (HPMC), carrageenan, xanthan gum, and
Carbopol were purchased from Sigma Aldrich. To prepare PCANS, gellan and pectin solutions were mixed in a
ratio of 1:1, followed by the addition of tween-80 (Sigma Aldrich). The solution was then supplemented with
benzalkonium chloride (BKC) (Sigma Aldrich) and subjected to immediate mixing by pipetting up and down
several times. Finally, phenethyl alcohol (Sigma Aldrich) was added, and the pH of the solution was adjusted to
5.5. For cell culture experiments and in vivo efficacy study, the individual components of PCANS were sterile
filtered using 0.2 µm PVDF syringe filters (EMD Millipore) and combined as described above.
Preparation of simulated nasal fluid (SNF) and simulated mucus: SNF was prepared by dissolving 1.32
g sodium chloride (150 mM), 447 mg potassium chloride (39.9 mM), and 88.5 mg calcium chloride (5.3 mM) in
150 mL ultrapure deionized sterile water and filtered using 0.2µm filter(68). The healthy simulated mucus was
formulated by dissolving 0.6 mg mucin from porcine stomach Type II (Sigma Aldrich), 0.8 mg mucin from porcine
stomach Type III (Sigma Aldrich), 0.32 mg bovine serum albumin (Sigma Aldrich) in 10 mL ultrapure deionized
water containing 20 mM HEPES buffer and 38 mM sodium chloride solution(69). The mixture was stirred
vigorously under slight heating to attain a homogenous solution.
Rheological measurements. Dynamic viscosity behavior of biopolymer solutions was evaluated using a
rotational rheometer (Discovery HR-2, TA Instruments) using a 40 mm diameter cone with a geometry angle of
- Samples were subjected to a linear shear rate ramp up to 40 s1 at 25o C to mimic the strain encountered by
the formulation when actuated through the nozzle of the spray device. The viscosity of the biopolymer solution
was measured during the upward ramp in triplicates. The sol-gel transition of biopolymer solutions with and
without the presence of SNF was evaluated by rotational rheology. The mechanical strength in terms of storage
modulus was assessed by applying amplitude sweep with a varying oscillatory strain at 1 Hz at 37o C.
Ex vivo** mucosal retention study**. Tissue harvested from sheep was cut open to expose the mucosal surface
and trimmed down to 75x26 mm. Mucosal tissue was then mounted on a glass slide facing upwards and
positioned at 450 to align it with the spray actuation angle. The tissue was initially moistened with SNF using a
generic nasal spray device, and excessive fluid was removed with sterile wipes. Brilliant green dye (Sigma
Aldrich) loaded polymeric solution was sprayed, keeping the spray nozzle tip at a distance of 5 cm from the slide
surface. The slides were examined for runoff/drip after 4 h of spraying. The distance traveled by the polymer
solution down the glass slide from the bottom end of formulation deposited on mucosal tissue was measured as
drip length. Drip length of free dye was considered 100%.
Cell culture. Madin-Darby canine kidney cells (ATCC®) were cultured in T-175 flasks (CELLTREAT) at 37oC
and 5% CO2 in DMEM (Gibco) supplemented with 10% fetal bovine serum (FBS) (Gibco) and 1% penicillin-
(streptomycin (Invitrogen). Hep2 cells and Vero E6 cells (ATCC®) were cultured at Integrated Biotherapeutics
(IBT) Bioservices in T-75 flasks at 37oC and 5% CO2 in EMEM supplemented with 10% FBS and 1% penicillin-
streptomycin. Human nasal epithelial cells (ATCC) were cultured in T-175 flasks at 37oC and 5% CO2 in EMEM
supplemented with 10% FBS and 1% penicillin-streptomycin.
Production of NanoLuc Luciferase expressing recombinant SARS-CoV-2. All replication-competent
SARS-CoV-2 experiments were performed in a BSL-3 facility at the Boston University National Emerging
infection, 50 µL of HKx31 Influenza A virus (H3N2, 5x1041x105 PFU/mL) (BEI Resources) in infection media
(serum-free DMEM containing 3 µg/mL TPCK-trypsin) was pre-treated with 50 µL of PCANS, biopolymer
solution, surfactant solution, alcohol solution or PBS. Samples were vortexed for 10 seconds and incubated at
37ºC for 10 or 60 min. After incubation, samples were centrifuged for 1 min at 1000 RPM, and the supernatant
was subjected to a 10-fold serial dilution until eighth dilution using infection medium. MDCK cells were then
exposed to pre-treated virus dilutions for 1 h. After infection, an overlay growth medium containing 2X DMEM
with 2% agarose (50:50) was poured onto the top of the cell monolayer and incubated for 72 h. The overlay was
removed, and cells were then fixed using 1 mL of 10% formalin and left for 1 h at room temperature, followed by
the addition of 1% crystal violet for 5-15 min. Wells were washed with water and left to dry out and PFUs were
counted to determine the viral titer.
In vitro** neutralization assay with SARS-CoV-2.** The day prior to infection experiment, 8x10⁴ Vero E6
cells/well were plated in a 24-well plate. To perform neutralization assay, 50 µL of PCANS, biopolymer solution,
surfactant solution, alcohol solution or PBS was mixed with 8x10⁴ PFU of SARS-CoV-2 mNG in 50 uL of infection
media (OptiMEM (Gibco) containing 3 µg/mL TPCK-trypsin), vortexed and centrifuged briefly prior to incubation
at 37ºC for 10 or 60 min. After incubation, samples were centrifuged for 1 min at 1000 RPM and serially diluted
10-fold until eighth dilution with infection medium. Of each dilution, 200 µL was then plated into a 24-well plate
and incubated for 1 h at 37°C prior addition of 800 µL of 1.2% Avicel (Dupont). Following a 24 h incubation period
at 37°C, Avicel was removed, cells were washed with 1X PBS and fixed for 3 h with 10% neutral buffered
formalin. Focal forming units (FFU) per mL were determined by counting NeonGreen expressing foci using an
Evos M5000 fluorescent microscope (Thermo Scientific).
In vitro** neutralization assay with adenovirus and respiratory syncytial virus.** The broad-spectrum
neutralization potency of PCANS was evaluated against adenovirus type 5 (ADV-5, ATCC, VR-2554™) and
respiratory syncytial virus strain A2 (RSV-A2, ATCC, VR-1540™) using plaque assay. Briefly, the day prior to
the infection, 1x10⁵ Vero E6 cells/well or 1.5x10⁵ Hep-2 cells/ well were plated in a 24-well plate for ADV-5 and
RSV-A2, respectively. On the day of infection, 50 µL of PCANS was mixed with 50 µL of virus (1 x10⁶ PFU/mL
of ADV-5 and 2x10⁶ PFU/mL of RSV-A2) in the infection media and incubated at 37ºC for 30 min. The pre-
treated mixture was 10-fold serially diluted in infection media after the incubation. Cells were washed with serum-
free media before infection and 200 µL of each dilution was transferred to the cells for a 1 h incubation prior to
the addition of a 1 mL overlay medium containing methylcellulose. Following a 72 h incubation, the overlay layer
was removed, and cells were fixed using 10% formalin with subsequent immunostaining for Vero E6 cells and
crystal violet staining for Hep-2 cells. Plaques were counted using a plaque reader (Bioreader-600-Va).
In vitro** neutralization assay with bacteria.** The neutralization potency of components and PCANS was
studied against gram-negative bacteria including Escherichia coli (E. coli) and K. pneumoniae. An overnight
culture of bacteria was prepared in 5 mL tryptic soy broth (TSB, Sigma Aldrich) media. On the day of the
experiment, bacteria suspension was adjusted to obtain an OD600nm = 0.2, which corresponds to 108 CFU/mL. A
50 µL of bacterial suspension in TSB media was incubated with 50 µL of PCANS, biopolymer solution, surfactant
solution or alcohol solution at 37oC for 10 or 60 min. After incubation, the sample/bacteria mixture was 10-fold
serially diluted in 1X PBS, and 10 µL of each dilution was plated onto pre-poured LB (Luria Broth, HiMedia
Laboratories Pvt Ltd) agar plates followed by an incubation of 16-18 h at 37oC, 5% CO2. The plates were then
counted for CFUs.
TEER assay and in vitro cytotoxicity of tween-80. RPMI 2650 cells were seeded on the apical part of
Transwell inserts (6.5 mm polyester membrane ~ 0.4 µm pore size, Corning) at a density of 1.5 x 10⁵ cells/cm2
in 0.1 mL EMEM. The basolateral compartment of the insert was filled with 0.6 mL EMEM media supplemented
with 10% FBS followed by incubation at 37oC. On day 4, the medium was removed from the top of the inserts,
and media volume in the bottom well was reduced to 200 µL. Every 2 days the medium was changed, and TEER
was measured. An epithelial volt ohmmeter (World Precision Instrument) was used to measure the impedance.
Until the monolayer formed with a constant impedance around 12, cells were grown with an air-liquid interface.
On day 12, TEER was measured prior to the treatment of cells with surfactants. 200 µL of medium containing
Triton X-100 (0.1% w/v) or tween-80 at different concentrations was added to the insert. Plate was incubated at
37ºC for 4 h. After incubation, wells were replenished with fresh medium, and TEER was measured after 4, 5,
12, and 24 h. The cytotoxic effect of tween-80 at different concentrations was also studied on RPMI 2650 cells.
Briefly, 20,000 cells/well were seeded in a 96-well plate and incubated at 37oC overnight to achieve 70-80%
confluency. Tween-80 solution in 0.2 mL EMEM media was added to the wells, followed by an incubation for 24
and 48 h. The metabolic activity of RPMI 2650 cells was measured using an XTT (2,3-bis(2-methoxy-4-nitro-5-
sulfophenyl)-2H-tetrazolium-5-carboxanilide) assay kit (ATCC®) according to the manufacturer’s protocol.
Capture of respiratory droplets. The inner surface of a glass twin impinger’s (Copley Scientific)
oropharyngeal region (denoted by red arrows in Fig.4a) was coated with SNF followed by spraying the gellan
and pectin mixture without or with different concentrations of tween-20, tween-80 or BKC using a VP3 nasal
spray pump (Aptar). Droplets with mass median aerodynamic diameter >5 µm and laden with rhodamine B-
loaded liposomes (size ~400 nm) were generated using a jet nebulizer. Nebulized droplets were administered
into the impinger under vacuum at a flow rate of 15 L/min for 3 min. The gel was retrieved, and fluorescence
intensity was quantified at an excitation and emission wavelength of 543 and 580 nm. Rhodamine B-loaded
liposomes were synthesized using the thin-film hydration method(71). Briefly, the lipids, DSPE-PEG (2000)
amine (Avanti Polar lipids), cholesterol (Sigma) and L-α-phosphatidylcholine, hydrogenated (Soy) (HPC, Avanti
Polar lipids) were dissolved in chloroform to prepare a 10mg/mL lipid stock solution in 1:1:3 molar ratio. A 2 mL
of lipid stock solution was added to a round-bottom flask containing 0.8 mL of rhodamine B isothiocyanate from
a 1mg/mL stock. The organic solvent was then evaporated using a rotary evaporator for 5 min to form a thin lipid
layer. The lipid film was then hydrated using 10 mL ultrapure water (Invitrogen) and silica glass beads were
added to the flask to suspend the lipid in the solution with vigorous shaking using the rotary evaporator at 40oC
for 45 min. The hydrated lipid suspension was sonicated (Probe sonicator) at 30% amplitude for 1 min with a
2sec pulse on and off condition. The size of liposomes was then analyzed using a Zeta Analyzer (Malvern).
To emulate the capture of pathogen-laden droplets in the human nasal cavity, a 3D transparent, silicone human
nose model (Koken Co, Ltd) was used. The anterior region of the Koken model was deposited with SNF followed
by the gellan and pectin mixture or PCANS with a single actuation using a nasal spray pump (Aptar). Koken
model was connected to a vacuum pump at an air flow rate of 15 L/min and rhodamine B-loaded liposomes were
then nebulized for 1 min. The model was disassembled to retrieve the formulation and captured dye-loaded
droplets after nebulization. The capture of droplets was measured by quantifying the fluorescence intensity at
an excitation and emission wavelength of 543 and 580 nm.
Spray characterization. Multi-dose nasal spray vials were filled with water or gellan solution or PCANS. The
pump (140 µL) with an insertion depth of 1.8 cm (Aptar) was used to study the spray characteristics including
plume geometry, spray plume, and droplet size distribution. Three replicate measurements were performed for 00 each sample. Plume geometry and spray pattern were measured using a Spray-View® measurement system 01 (Proveris Scientific, Hudson, MA) at a distance of 30 mm from the nozzle orifice of the actuator. This acquisition
In vivo** biodistribution and nasal retention**. Nasal retention of the formulation was performed in mice.
Briefly, C57BL/6 mice were administered with 10 µL per nostril of free DiR (Thermofisher) or PCANS mixed with
DiR at a final concentration of 10 µg/ml). Mice were euthanized at different time points and nasal cavity was
harvested and imaged using IVIS (Bruker’s In-Vivo Xtreme optical and x-ray in vivo imaging system) at an
excitation and emission wavelength of 680/700 nm. Vital organs such as lung, liver, spleen, kidney, and heart,
were also imaged at 2 and 24 h time points. To determine the mechanism of long residence time, animals were
intranasally instilled with DiR-mixed gellan and pectin mixture without or with BKC and tween-80. After 8 h,
animals were euthanized to harvest and image the nasal cavity using Perkin Elmer IVIS Lumina II and the total
flux was expressed in (p/sec/m2/sr).
In vivo** prophylactic activity of PCANS.** Mice were intranasally instilled with 10 µL PCANS or PBS into
each nostril under brief anesthesia using isoflurane. After 15 min, animals were challenged with 250 or 500 PFU
of PR8 intranasally. One cohort of animals was followed for body weight changes and survival for a period of 10
days. Animals were euthanized when the body weight was reduced to 20%. Animals from a second cohort were
euthanized either on day 2 or 4 after infection to enumerate lung viral titer, inflammatory cell count in
bronchoalveolar lavage (BAL) fluid, and inflammatory cytokine levels in lung homogenate. BAL fluid was isolated
by gently instilling saline solution into bronchioles with a catheter inserted through the trachea. The total cells
and immune cell types from the collected BAL fluid were quantified using Diff-quik kit as per manufacturer’s
protocol. For lung viral titer and cytokine profiling, left lung was homogenized and centrifuged at 2000 g for 10
min at 4oC to collect the supernatant. The obtained supernatant was further used for downstream assays. Viral
titer was enumerated using plaque assay with MDCK cells, as detailed above. Cytokine profiling was performed
using respective ELISA kits of IL-6, TNF-a, and IL-1� (BioLegend®) according to the manufacturer’s protocol.
Histopathology of the right lung was determined using hematoxylin and eosin staining, and inflammation scoring
was performed as reported previously(73).
Statistics
- Statistical analysis and graphing were conducted using Graphpad Prism. A one-way ANOVA with Tukey's
- post hoc analysis was used to compare multiple groups. Two-way ANOVA with Tukey’s multiple comparison
- tests was used to analyze the data with two variables. To evaluate the efficiency of PCANS, survival plots were
- generated using the Kaplan-Meier survival curve, and the statistical significance of the results was analyzed
- using the Gehan-Breslow-Wilcoxon test. P values for the body weight changes were determined using one-way
- ANOVA with Brown-Forsythe post hoc analysis. A Pvalue of less than 0.05 was considered statistically
- significant.
Acknowledgments
- We acknowledge funding support from Gillian Reny Stepping Strong Center for Trauma Innovation at the
- Brigham and Women’s Hospital (to NJ and JMK), Startup Funds from the Department of Anesthesiology,
- Perioperative, and Pain Medicine at the Brigham and Women’s Hospital (to NJ), Fulbright-Nehru Postdoctoral
- Fellowship (to JJ), and Boston University (to FD) and the Peter Paul Career Development Award (to FD). The
- metered dose spray pumps were generously gifted by Aptar Inc. We acknowledge Integrated BioTherapeutics
- (IBT) Bioservices for evaluating the neutralization activity of PCANS against RSV and adenovirus, and Proveris
- Scientific for characterizing the spray patterns.
Author contribution
- Conceptualization: J.J., H.M.B., J.R.Q., Y.T., J.M.K., N.J. Data curation: J.J, H.M.B., J.R.Q., D.K., E.B. Data
- analysis: J.J., H.M.B., J.R.Q., D.K., E.B. Funding acquisition: J.M.K., N.J. Investigation: J.J., H.M.B., J.R.Q.,
- Y.M., E.B., P.S., K.S., O.S., R.N., E.A., S.R., J.K. Methodology: J.J., H.M.B., J.R.Q., D.K., S.K., X.L.L., J.M.,
- J.G., J.N.L, A.Y., F.D. Project Administration: Y.T., J.M.K., N.J. Supervision: F.D., Y.T., J.M.K., N.J. Validation:
- J.J., H.M.B., J.R.Q., J.M.K., N.J. Manuscript Writing - original draft: J.J., H.M.B., S.R., N.J., Manuscript Editing:
- J.J., H.M.B., D.K., F.D., Y.T., J.M.K, N.J.
Competing interests
- J.J., H.M.B, Y.T., and J.M.K have one pending patent based on the PCANS formulation described in this
- manuscript. N.J. and J.M.K are paid consultants, scientific advisory board members, and hold equity in Akita
- Bio, a company that has licensed IP generated by N.J. that may benefit financially if the IP is further validated.
- The interests of N.J. were reviewed and are subject to a management plan overseen by his institution in
- accordance with its conflict of interest policies. J.M.K has been a paid consultant and or equity holder for multiple
- companies (listed here: https://www.karplab.net/team/jeff-karp (opens in a new tab))). (opens in a new tab))
References
- Estimates of the global, regional, and national morbidity, mortality, and aetiologies of lower respiratory
- infections in 195 countries, 1990-2016: a systematic analysis for the Global Burden of Disease Study
- Lancet Infect Dis. 18, 1191–1210 (2018).
- M. K. Hossain, M. Hassanzadeganroudsari, V. Apostolopoulos, The emergence of new strains of SARS-
- CoV-2. What does it mean for COVID-19 vaccines? Expert Rev Vaccines. 20, 635–638 (2021).
- J. L. Excler, M. Saville, S. Berkley, J. H. Kim, Vaccine development for emerging infectious diseases. Nat
88 Med. 27 (2021), pp. 591–600.
- E. V. Bailey, F. A. Wilson, Vaccine Uptake in the US after Full Food and Drug Administration Approval of
- the BNT162b2 mRNA COVID-19 Vaccine. JAMA Netw Open. 5 (2022), p. E226108.
- O. J. Watson, G. Barnsley, J. Toor, A. B. Hogan, P. Winskill, A. C. Ghani, Global impact of the first year
- of COVID-19 vaccination: a mathematical modelling study. Lancet Infect Dis. 22, 1293–1302 (2022).
- J. Joseph, Harnessing Nasal Immunity with IgA to Prevent Respiratory Infections. Immuno. 2, 571–583
94 (2022).
- M. G. Thompson, J. L. Burgess, A. L. Naleway, H. Tyner, S. K. Yoon, J. Meece, L. E. W. Olsho, A. J.
- Caban-Martinez, A. L. Fowlkes, K. Lutrick, H. C. Groom, K. Dunnigan, M. J. Odean, K. Hegmann, E.
- Stefanski, L. J. Edwards, N. Schaefer-Solle, L. Grant, K. Ellingson, J. L. Kuntz, T. Zunie, M. S. Thiese, L.
- Ivacic, M. G. Wesley, J. Mayo Lamberte, X. Sun, M. E. Smith, A. L. Phillips, K. D. Groover, Y. M. Yoo, J.
- Gerald, R. T. Brown, M. K. Herring, G. Joseph, S. Beitel, T. C. Morrill, J. Mak, P. Rivers, B. P. Poe, B. 00 Lynch, Y. Zhou, J. Zhang, A. Kelleher, Y. Li, M. Dickerson, E. Hanson, K. Guenther, S. Tong, A. Bateman, 01 E. Reisdorf, J. Barnes, E. Azziz-Baumgartner, D. R. Hunt, M. L. Arvay, P. Kutty, A. M. Fry, M. Gaglani, 02 Prevention and Attenuation of Covid-19 with the BNT162b2 and mRNA-1273 Vaccines. New England 03 Journal of Medicine. 385, 320–329 (2021).
- C. C. Wang, K. A. Prather, J. Sznitman, J. L. Jimenez, S. S. Lakdawala, Z. Tufekci, L. C. Marr, Airborne
- transmission of respiratory viruses. Science (1979). 373 (2021), , doi:10.1126/science.abd9149.
- J. H. Ahn, J. M. Kim, S. P. Hong, S. Y. Choi, M. J. Yang, Y. S. Ju, Y. T. Kim, H. M. Kim, T. Rahman, M.
- K. Chung, S. D. Hong, H. Bae, C. S. Lee, G. Y. Koh, Nasal ciliated cells are primary targets for SARS- 08 CoV-2 replication in the early stage of COVID-19. Journal of Clinical Investigation. 131 (2021), 09 doi:10.1172/JCI148517.
- W. Sungnak, N. Huang, C. Bécavin, M. Berg, R. Queen, M. Litvinukova, C. Talavera-López, H. Maatz, D.
- Reichart, F. Sampaziotis, K. B. Worlock, M. Yoshida, J. L. Barnes, N. E. Banovich, P. Barbry, A. Brazma,
- J. Collin, T. J. Desai, T. E. Duong, O. Eickelberg, C. Falk, M. Farzan, I. Glass, R. K. Gupta, M. Haniffa, P.
- Horvath, N. Hubner, D. Hung, N. Kaminski, M. Krasnow, J. A. Kropski, M. Kuhnemund, M. Lako, H. Lee,
- S. Leroy, S. Linnarson, J. Lundeberg, K. B. Meyer, Z. Miao, A. V. Misharin, M. C. Nawijn, M. Z. Nikolic,
- M. Noseda, J. Ordovas-Montanes, G. Y. Oudit, D. Pe’er, J. Powell, S. Quake, J. Rajagopal, P. R. Tata, E.
- L. Rawlins, A. Regev, P. A. Reyfman, O. Rozenblatt-Rosen, K. Saeb-Parsy, C. Samakovlis, H. B. Schiller,
- J. L. Schultze, M. A. Seibold, C. E. Seidman, J. G. Seidman, A. K. Shalek, D. Shepherd, J. Spence, A.
- Spira, X. Sun, S. A. Teichmann, F. J. Theis, A. M. Tsankov, L. Vallier, M. van den Berge, J. Whitsett, R.
- Xavier, Y. Xu, L. E. Zaragosi, D. Zerti, H. Zhang, K. Zhang, M. Rojas, F. Figueiredo, SARS-CoV-2 entry
- factors are highly expressed in nasal epithelial cells together with innate immune genes. Nat Med. 26,
- 681–687 (2020).
- A. B. Patel, A. Verma, Nasal ACE2 Levels and COVID-19 in Children. JAMA - Journal of the American
23 Medical Association. 323 (2020), pp. 2386–2387.
- Y. J. Hou, K. Okuda, C. E. Edwards, D. R. Martinez, T. Asakura, K. H. Dinnon, T. Kato, R. E. Lee, B. L.
Yount, T. M. Mascenik, G. Chen, K. N. Olivier, A. Ghio, L. V. Tse, S. R. Leist, L. E. Gralinski, A. Schäfer,
H. Dang, R. Gilmore, S. Nakano, L. Sun, M. L. Fulcher, A. Livraghi-Butrico, N. I. Nicely, M. Cameron, C.
Cameron, D. J. Kelvin, A. de Silva, D. M. Margolis, A. Markmann, L. Bartelt, R. Zumwalt, F. J. Martinez,
S. P. Salvatore, A. Borczuk, P. R. Tata, V. Sontake, A. Kimple, I. Jaspers, W. K. O’Neal, S. H. Randell,
R. C. Boucher, R. S. Baric, SARS-CoV-2 Reverse Genetics Reveals a Variable Infection Gradient in the
Respiratory Tract. Cell. 182, 429-446.e14 (2020).
- B. Xia, X. Pan, R. H. Luo, X. Shen, S. Li, Y. Wang, X. Zuo, Y. Wu, Y. Guo, G. Xiao, Q. Li, X. Y. Long, X.
Y. He, H. Y. Zheng, Y. Lu, W. Pang, Y. T. Zheng, J. Li, L. K. Zhang, Z. Gao, Extracellular vesicles mediate
antibody-resistant transmission of SARS-CoV-2. Cell Discov. 9 (2023), doi:10.1038/s41421-022-00510-
- S. Baur, M. Rautenberg, M. Faulstich, T. Grau, Y. Severin, C. Unger, W. H. Hoffmann, T. Rudel, I. B.
Autenrieth, C. Weidenmaier, A Nasal Epithelial Receptor for Staphylococcus aureus WTA Governs
Adhesion to Epithelial Cells and Modulates Nasal Colonization. PLoS Pathog. 10 (2014),
doi:10.1371/journal.ppat.1004089.
- J. N. Weiser, D. M. Ferreira, J. C. Paton, Streptococcus pneumoniae: Transmission, colonization and
invasion. Nat Rev Microbiol. 16 (2018), pp. 355–367.
- N. Ivanova, Y. Sotirova, G. Gavrailov, K. Nikolova, V. Andonova, Advances in the Prophylaxis of
Respiratory Infections by the Nasal and the Oromucosal Route: Relevance to the Fight with the SARS-
CoV-2 Pandemic. Pharmaceutics. 14 (2022), , doi:10.3390/pharmaceutics14030530.
- S. Williamson, L. Dennison, K. Greenwell, J. Denison-Day, F. Mowbray, S. Richards-Hall, D. Smith, K.
Bradbury, B. Ainsworth, P. Little, A. W. A. Geraghty, L. Yardley, Using nasal sprays to prevent respiratory
tract infections: a qualitative study of online consumer reviews and primary care patient interviews. BMJ
Open. 12 (2022), doi:10.1136/bmjopen-2021-059661.
- M. Morokutti-Kurz, M. Fröba, P. Graf, M. Große, A. Grassauer, J. Auth, U. Schubert, E. Prieschl-
Grassauer, Iota-carrageenan neutralizes SARS-CoV-2 and inhibits viral replication in vitro. PLoS One. 16
(2021), doi:10.1371/journal.pone.0237480.
- S. Frank, S. M. Brown, J. A. Capriotti, J. B. Westover, J. S. Pelletier, B. Tessema, In Vitro Efficacy of a
Povidone-Iodine Nasal Antiseptic for Rapid Inactivation of SARS-CoV-2. JAMA Otolaryngol Head Neck
Surg. 146, 1054–1058 (2020).
- M. Tandon, W. Wu, K. Moore, S. Winchester, Y.-P. Tu, C. Miller, R. Kodgule, A. Pendse, S. Rangwala, S.
Joshi, S. Group, SARS-CoV-2 accelerated clearance using a novel nitric oxide nasal spray (NONS)
treatment: A randomized trial (2022), doi:10.1016/j.
- A. Leibbrandt, C. Meier, M. König-Schuster, R. Weinmüllner, D. Kalthoff, B. Pflugfelder, P. Graf, B. Frank-
Gehrke, M. Beer, T. Fazekas, H. Unger, E. Prieschl-Grassauer, A. Grassauer, Iota-carrageenan is a
potent inhibitor of influenza a virus infection. PLoS One. 5 (2010), doi:10.1371/journal.pone.0014320.
- Y. Lin, S. Yue, Y. Yang, S. Yang, Z. Pan, X. Yang, L. Gao, J. Zhou, Z. Li, L. Hu, J. Tang, Q. Wu, S. Lei,
Q. Tian, Y. Wang, Y. Hao, L. Xu, Q. Huang, B. Zhu, Y. Chen, X. Chen, L. Ye, Nasal Spray of Neutralizing
Monoclonal Antibody 35B5 Confers Potential Prophylaxis Against Severe Acute Respiratory Syndrome
Coronavirus 2 Variants of Concern: A Small-Scale Clinical Trial. Clinical Infectious Diseases. 76, E336–
E341 (2023).
- D. Balmforth, J. A. Swales, L. Silpa, A. Dunton, K. E. Davies, S. G. Davies, A. Kamath, J. Gupta, S. Gupta,
M. A. Masood, Á. McKnight, D. Rees, A. J. Russell, M. Jaggi, R. Uppal, Evaluating the efficacy and safety
of a novel prophylactic nasal spray in the prevention of SARS-CoV-2 infection: A multi-centre, double
blind, placebo-controlled, randomised trial. Journal of Clinical Virology. 155 (2022),
- J. M. Figueroa, M. E. Lombardo, A. Dogliotti, L. P. Flynn, R. Giugliano, G. Simonelli, R. Valentini, A.
Ramos, P. Romano, M. Marcote, A. Michelini, A. Salvado, E. Sykora, C. Kniz, M. Kobelinsky, D. M.
Salzberg, D. Jerusalinsky, O. Uchitel, Efficacy of a nasal spray containing iota-carrageenan in the
postexposure prophylaxis of COVID-19 in hospital personnel dedicated to patients care with COVID-19
disease. Int J Gen Med. 14, 6277–6286 (2021).
- A. Frediansyah, The antiviral activity of iota-, kappa-, and lambda-carrageenan against COVID-19: A
critical review. Clin Epidemiol Glob Health. 12 (2021), , doi:10.1016/j.cegh.2021.100826.
- Preservative Efficacy Tests in Formulated Nasal Products: Reproducibility and Factors Affecting
Preservative Activity. J. Pharm. Pharmacol. 48, 19 (1996).
- R. C. Rowe, P. J. Sheskey, W. G. Cook, M. E. Fenton, Eds., Handbook of Pharmaceutical Excipients
(Pharmaceutical Press, 2012, ed. 7;
J).
- S. Rugonyi, S. C. Biswas, S. B. Hall, The biophysical function of pulmonary surfactant. Respir Physiol
33 Neurobiol. 163, 244–255 (2008).
- G. W. Hallworth, D. G. Westmoreland, The twin impinger: a simple device for assessing the delivery of
- drugs from metered dose pressurized aerosol inhalers. Journal of Pharmacy and Pharmacology. 39, 966–
- 972 (1987).
- A. Cidem, P. Bradbury, D. Traini, H. X. Ong, Modifying and Integrating in vitro and ex vivo Respiratory
- Models for Inhalation Drug Screening. Front Bioeng Biotechnol. 8 (2020), ,
- doi:10.3389/fbioe.2020.581995.
- H. Y. Choi, Y. H. Lee, C. H. Lim, Y. S. Kim, I. S. Lee, J. M. Jo, H. Y. Lee, H. G. Cha, H. J. Woo, D. S. Seo,
- Assessment of respiratory and systemic toxicity of Benzalkonium chloride following a 14-day inhalation
- study in rats. Part Fibre Toxicol. 17 (2020), doi:10.1186/s12989-020-0339-8.
- B. Marple, P. Roland, M. Benninger, Safety review of benzalkonium chloride used as a preservative in
- intranasal solutions: An overview of conflicting data and opinions. Otolaryngology - Head and Neck
- Surgery. 130 (2004), pp. 131–141.
- P. G. Djupesland, J. C. Messina, R. A. Mahmoud, "Role of nasal casts for in vitro evaluation of nasal drug
- delivery and quantitative evaluation of various nasal casts" in Therapeutic Delivery (Newlands Press Ltd,
- 2020), vol. 11, pp. 485–495.
- S. Gizurarson, The Effect of Cilia and the Mucociliary Clearance on Successful Drug Delivery. Biol. Pharm.
50 Bull. 38, 497–506 (2015).
- J. D. Ehrick, S. A. Shah, C. Shaw, V. S. Kulkarni, I. Coowanitwong, S. De, J. D. Suman, "Considerations
- for the Development of Nasal Dosage Forms" in Sterile Product Development (Nature Publishing Group,
- 2013; http://link.springer.com/10.1007/978-1-4614-7978-9_5), (opens in a new tab)) vol. 6, pp. 99–144.
- V. Kulkarni, C. Shaw, “Formulation and characterization of nasal sprays” (2012), (available at
- www.inhalationmag.com). (opens in a new tab)
- M. Fukushi, T. Ito, T. Oka, T. Kitazawa, T. Miyoshi-Akiyama, T. Kirikae, M. Yamashita, K. Kudo, Serial
- histopathological examination of the lungs of mice infected with influenza A virus PR8 strain. PLoS One.
- 6 (2011), doi:10.1371/journal.pone.0021207.
- A. T. Harding, G. D. HaasI, B. S. Chambers, N. S. Heaton, Influenza viruses that require 10 genomic
- segments as antiviral therapeutics. PLoS Pathog. 15 (2019), doi:10.1371/journal.ppat.1008098.
- N. Gonzalez-Juarbe, A. N. Riegler, A. S. Jureka, R. P. Gilley, J. D. Brand, J. E. Trombley, N. R. Scott, M.
- P. Platt, P. H. Dube, C. M. Petit, K. S. Harrod, C. J. Orihuela, Influenza-Induced Oxidative Stress
- Sensitizes Lung Cells to Bacterial-Toxin-Mediated Necroptosis. Cell Rep. 32 (2020),
- doi:10.1016/j.celrep.2020.108062.
- D. Gowda, M. Ohno, S. G. Siddabasave, H. Chiba, M. Shingai, H. Kida, S. P. Hui, Defining the kinetic
- effects of infection with influenza virus A/PR8/34 (H1N1) on sphingosine-1-phosphate signaling in mice
- by targeted LC/MS. Sci Rep. 11 (2021), doi:10.1038/s41598-021-99765-0.
- X. He, C. He, W. Hong, J. Yang, X. Wei, Research progress in spike mutations of SARS-CoV-2 variants
- and vaccine development. Med Res Rev. 43 (2023), pp. 932–971.
- D. Planas, N. Saunders, P. Maes, F. Guivel-Benhassine, C. Planchais, J. Buchrieser, W. H. Bolland, F.
- Porrot, I. Staropoli, F. Lemoine, H. Péré, D. Veyer, J. Puech, J. Rodary, G. Baele, S. Dellicour, J.
- Raymenants, S. Gorissen, C. Geenen, B. Vanmechelen, T. Wawina -Bokalanga, J. Martí-Carreras, L.
- Cuypers, A. Sève, L. Hocqueloux, T. Prazuck, F. A. Rey, E. Simon-Loriere, T. Bruel, H. Mouquet, E.
- André, O. Schwartz, Considerable escape of SARS-CoV-2 Omicron to antibody neutralization. Nature.
- 602, 671–675 (2022).
- M. L. Cannon, J. B. Westover, R. Bleher, M. A. Sanchez-Gonzalez, G. Ferrer, In Vitro Analysis of the Anti-
- viral Potential of nasal spray constituents against SARS-CoV-2. bioRxiv preprint (2020),
- doi:10.1101/2020.12.02.408575.
- Z. Ku, X. Xie, P. R. Hinton, X. Liu, X. Ye, A. E. Muruato, D. C. Ng, S. Biswas, J. Zou, Y. Liu, D. Pandya,
- V. D. Menachery, S. Rahman, Y. A. Cao, H. Deng, W. Xiong, K. B. Carlin, J. Liu, H. Su, E. J. Haanes, B.
- A. Keyt, N. Zhang, S. F. Carroll, P. Y. Shi, Z. An, Nasal delivery of an IgM offers broad protection from
- SARS-CoV-2 variants. Nature. 595, 718–723 (2021).
- C. Bogdan, Nitric oxide and the immune response. Nat Immunol. 2, 907–916 (2001).
- F. Lisi, A. N. Zelikin, R. Chandrawati, Nitric Oxide to Fight Viral Infections. Advanced Science. 8, 2003895
85 (2021).
- M. Tandon, W. Wu, K. Moore, S. Winchester, Y.-P. Tu, C. Miller, R. Kodgule, A. Pendse, S. Rangwala, S.
Joshi, SARS-CoV-2 accelerated clearance using a novel nitric oxide nasal spray (NONS) treatment: A
randomized trial. The Lancet regional health. Southeast Asia. 3, 100036 (2022).
- S. Gizurarson, Animal models for intranasal drug delivery studies: A review article. Acta Pharm Nord. 2, 90 105–122 (1990).
- X. Mei, J. Li, Z. Wang, D. Zhu, K. Huang, S. Hu, K. D. Popowski, K. Cheng, An inhaled bioadhesive
hydrogel to shield non-human primates from SARS-CoV-2 infection. Nat Mater. 22, 903–912 (2023).
- U. C. Galgatte, A. B. Kumbhar, P. D. Chaudhari, Development of in situ gel for nasal delivery: Design,
optimization, in vitro and in vivo evaluation. Drug Deliv. 21, 62–73 (2014).
- R. Hamed, J. Fiegel, Synthetic tracheal mucus with native rheological and surface tension properties. J
96 Biomed Mater Res A. 102, 1788–1798 (2014).
- X. Xie, A. E. Muruato, X. Zhang, K. G. Lokugamage, C. R. Fontes-Garfias, J. Zou, J. Liu, P. Ren, M.
- Balakrishnan, T. Cihlar, C. T. K. Tseng, S. Makino, V. D. Menachery, J. P. Bilello, P. Y. Shi, A
- nanoluciferase SARS-CoV-2 for rapid neutralization testing and screening of anti-infective drugs for
00 COVID-19. Nat Commun. 11 (2020), doi:10.1038/s41467-020-19055-7.
01 71. H. Zhang, Thin-Film Hydration Followed by Extrusion Method for Liposome Preparation. Methods Mol
02 Biol. 1522, 17–22 (2017).
03 72. D. J. Farina, "Regulatory Aspects of Nasal and Pulmonary Spray Drug Products" in Handbook of Non- 04 Invasive Drug Delivery Systems (Elsevier, 2010; 05 https://linkinghub.elsevier.com/retrieve/pii/B9780815520252100101 (opens in a new tab)), pp. 247–290. 06 73. S. Awasthi, N. Rahman, B. Rui, G. Kumar, V. Awasthi, M. Breshears, S. Kosanke, Lung and general 07 health effects of Toll-like receptor-4 (TLR4)-interacting SPA4 peptide. BMC Pulm Med. 20 (2020), 08 doi:10.1186/s12890-020-01187-7.
09
10
11
12
13
14
15
16
17
18
19
20
21
22
23
24
25
26
27
28
Figures
30
Fig. 1: Pathogen Capture and Neutralizing Spray (PCANS) acts via a multi-pronged approach against
- respiratory pathogens. An aqueous, “drug-free” solution of PCANS, comprising mucoadhesive biopolymers,
- surfactants, and alcohol, is administered using a pocket-sized nasal spray device and undergoes a phase
- transition to form a hydrogel layer over nasal mucosa. Surfactants in PCANS reduce interfacial tension of the
- nasal lining and increase wettability to enhance the capture or reduce the bounce-off of pathogen-laden
- respiratory droplets from the inhaled air. PCANS layers as a physical barrier preventing the transport of
- pathogens through the nasal lining. Finally, pathogens are neutralized by biopolymers and surfactants present
- in PCANS. PCANS is cleared via the native mucosal clearance mechanism and is eliminated through the
- digestive route.
Fig. 2: Biopolymers were screened for physical barrier property against pathogen entry. Viscosity as a
- function of shear rate up to 40 s1 at 25oC for different concentrations of (a) gellan, (b) pectin, (c) hydroxy propyl
- methyl cellulose (HPMC), (d) carboxymethylcellulose (CMC), (e) Carbopol and (f) xanthan gum in water. The
- sprayable viscosity window is shown below the dashed line. (g) Storage modulus (G’) of 0.4% (w/v) gellan, 2%
- (w/v) pectin, 0.5% (w/v) HPMC, 0.5% (w/v) CMC, 0.2% (w/v) Carbopol, and 0.2% (w/v) xanthan gum, without
- and with simulated nasal fluid (SNF). Amplitude sweep measurements were performed at 37oC by varying
- oscillatory strain between 0.005% to 10 % at 1 Hz frequency. ****P < 0.0001, *P < 0.05. n.s., not significant. (h)
- Amount of Influenza A virus (IAV) that permeated within 4 h through a simulated nasal fluid (SNF)-coated cell
- strainer (pore size ~70 µm) or a cell strainer coated with simulated mucus/SNF mixture or a biopolymer/SNF
- mixture. Permeation of viral particles was quantified by evaluating the viral titer in the chamber below the strainer
- using plaque assay performed in MDCK host cells. Results are expressed in plaque-forming units (PFU/mL).
- P* < 0.01, *P < 0.05 compared to mucus/SNF, n.s, not significant.** Percentage permeation of a fluorescent dye,
- rhodamine B isothiocyanate through (i) an SNF-coated cell strainer or a cell strainer coated with simulated
- mucus/SNF mixture or a biopolymer/SNF mixture. ****P < 0.0001 compared to mucus/SNF and (j) an SNF-
- coated strainer or strainer coated with gellan/SNF at different concentrations of gellan. ****P < 0.0001 compared
- to 0.05% w/v gellan/SNF. (k) Percentage drip length of free brilliant green dye or mucoadhesive polymers mixed
- with brilliant green dye on porcine mucosal tissue. Drip length from the spray area was measured as the distance
- traversed in 4 h by the biopolymer or free dye from the point of deposition. The percentage drip length of each
- biopolymer was calculated with respect to the drip length of the free dye. ****P < 0.0001 compared to free dye.
- For g and h, Pvalues were determined using two-way ANOVA with Tukey’s multiple comparisons tests. For i-
- k, Pvalues were determined using one-way ANOVA with Tukey’s post hoc analysis. Data in a-f are from a single
- experiment (experiment repeated three times). Data in g-k are means ± SD of technical repeats (n = 3, each
- experiment performed at least twice).
64
65
66
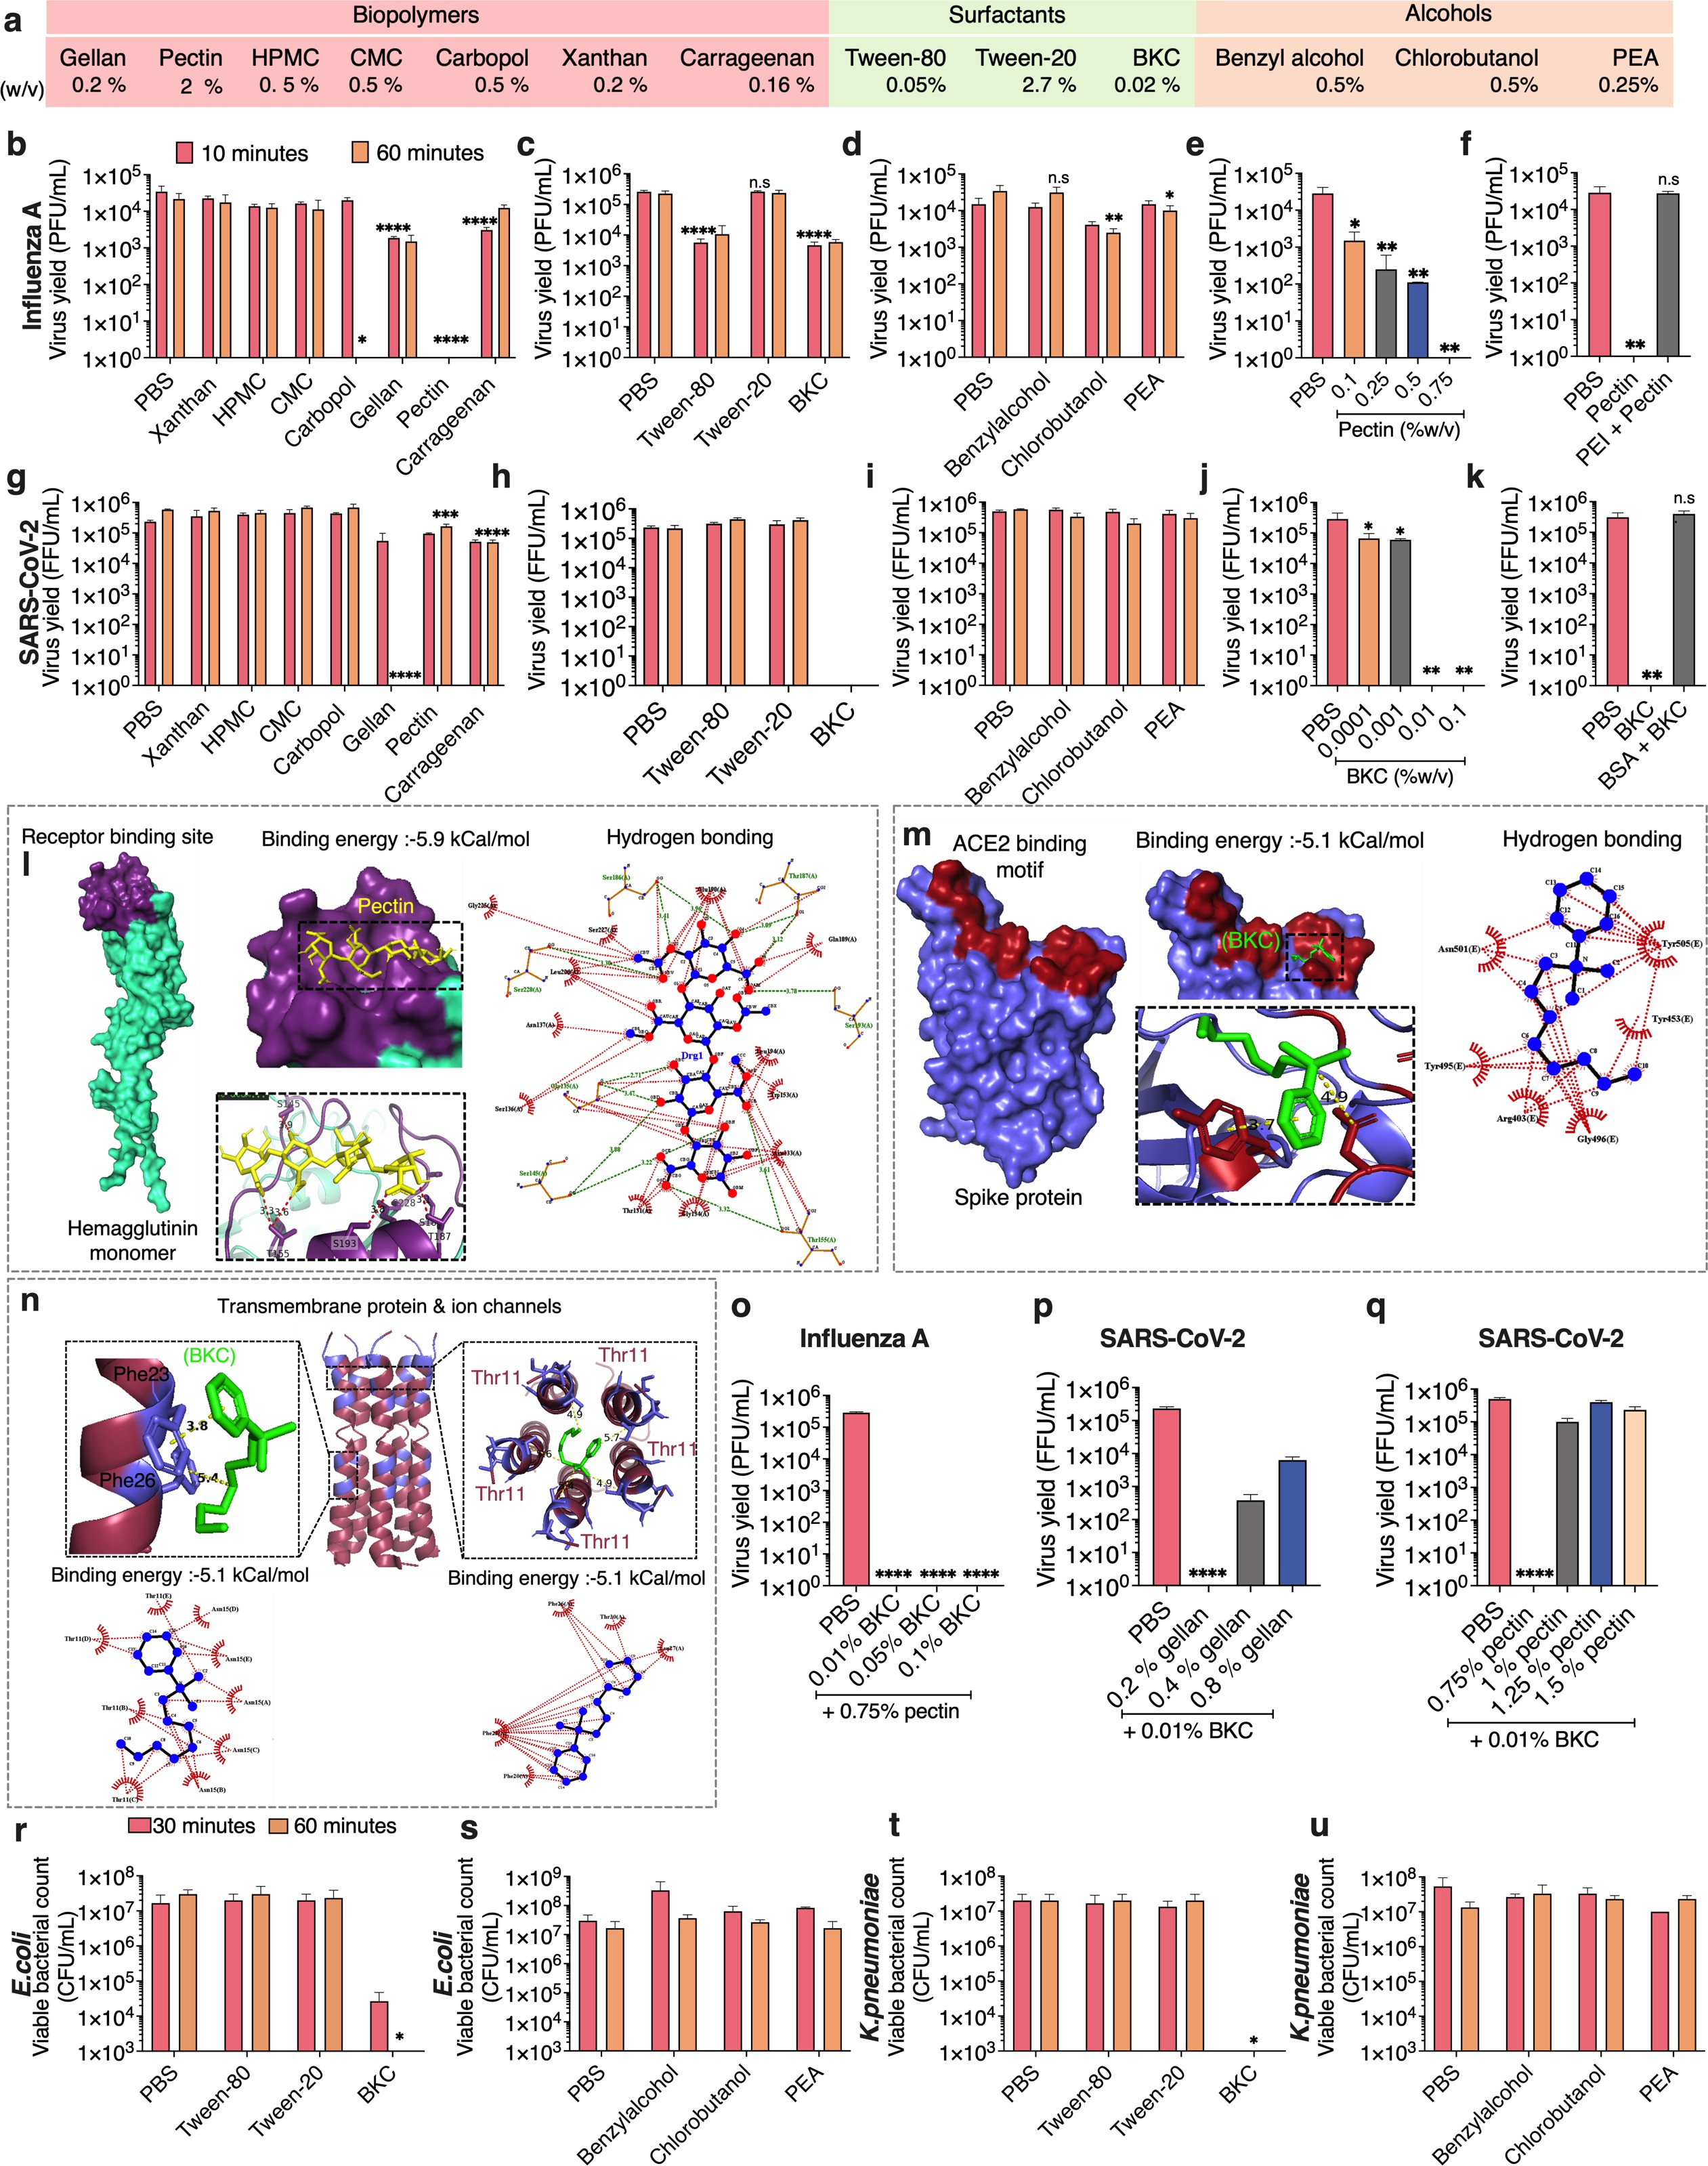
Fig. 3: Biopolymers, surfactants and alcohols were screened for neutralization of different respiratory
- pathogens. (a) Table summarizes different components and their concentrations to determine the neutralization
- ability against respiratory pathogens. Each component was individually evaluated for its pathogen neutralization
- potential. IAV and SARS-CoV-2 viral loads in the host cells after 10 or 60 min incubation of the virus with (b, g)
- different biopolymers, (c, h) different surfactants, and (d, i) different alcohols. Viable viral titer was quantified
- using plaque assay in MDCK host cells for IAV and focus-forming assay in Vero E6 cells for SARS-CoV-2 virus.
- Results are expressed in plaque-forming units (PFU/mL) or focus-forming units (FFU/mL). ****P < 0.0001, ***P
- < 0.001, **P < 0.01, *P < 0.05 compared to 10 minutes of incubation with PBS. n.s, not significant. Viral loads in
- the host cells after 10 min incubation of (e) IAV and (j) SARS-CoV-2 with different concentrations of pectin and
- BKC, respectively. **P < 0.01, *P < 0.05 compared to PBS. Viral loads in the host cells after 10 min incubation
- of (f) IAV and (k) SARS-CoV-2 with pectin + polyethylenimine and BKC + bovine serum albumin, respectively.
- *P<0.01 compared to PBS. n.s, not significant. (l) Pectin (yellow) binds to the receptor binding site of IAV
- (purple) at the distal part of hemagglutinin monomer (colored in purple) through hydrophobic interactions with
- Ser227 and Glu190, and hydrogen bonding with Ser228, Ser186, and Thr187. Blue and red dots in hydrogen
- bonding maps represent carbon and oxygen atoms, respectively. (m) Chemical interaction of BKC (green) with
- ACE2 binding motif (red) in the spike protein of SARS-CoV-2. Interaction map reveals the hydrogen bonding of
- BKC with Tyr505 and Gly496. (n) Aromatic pi-pi interaction of BKC (green) with Phe23 (purple) in the
- transmembrane domain and with Thr11 (brown) membrane helices. Interaction analysis shows 10 hydrophobic
- bonds with Phe23 and 8 hydrophobic bonds with Phe26. (o) Viral load in host cells after 10 min incubation of
- IAV with pectin in the presence of different concentrations of BKC. ****P < 0.0001 compared to PBS. Viral load
- in the host cells after 10 min incubation of SARS-CoV-2 with BKC (0.01% w/v) in the presence of different
- concentrations of (p) gellan and (q) pectin. ****P < 0.0001 compared to PBS. Effect of surfactants (r, t) and
- alcohols (s, u) against gram-negative bacteria E. coli and K. pneumoniae using colony-forming unit (CFU) plate
- count method after 30 and 60 minutes of exposure. Viable bacterial colonies are expressed in CFU/mL. *P<0.05
- compared to PBS. For b-d, P values were determined using two-way ANOVA with Tukey’s post hoc analysis.
- For e, f, j, k, o-q, P values were determined using one-way ANOVA. Data in b-k and o-u are presented as
- Means ± S.D of technical repeats (n = 3, each experiment performed at least twice). Ser, serine; Thr, threonine;
- Glu, glutamic acid; Phe, phenylalanine; Tyr, tyrosine; Gly, glycine.
96
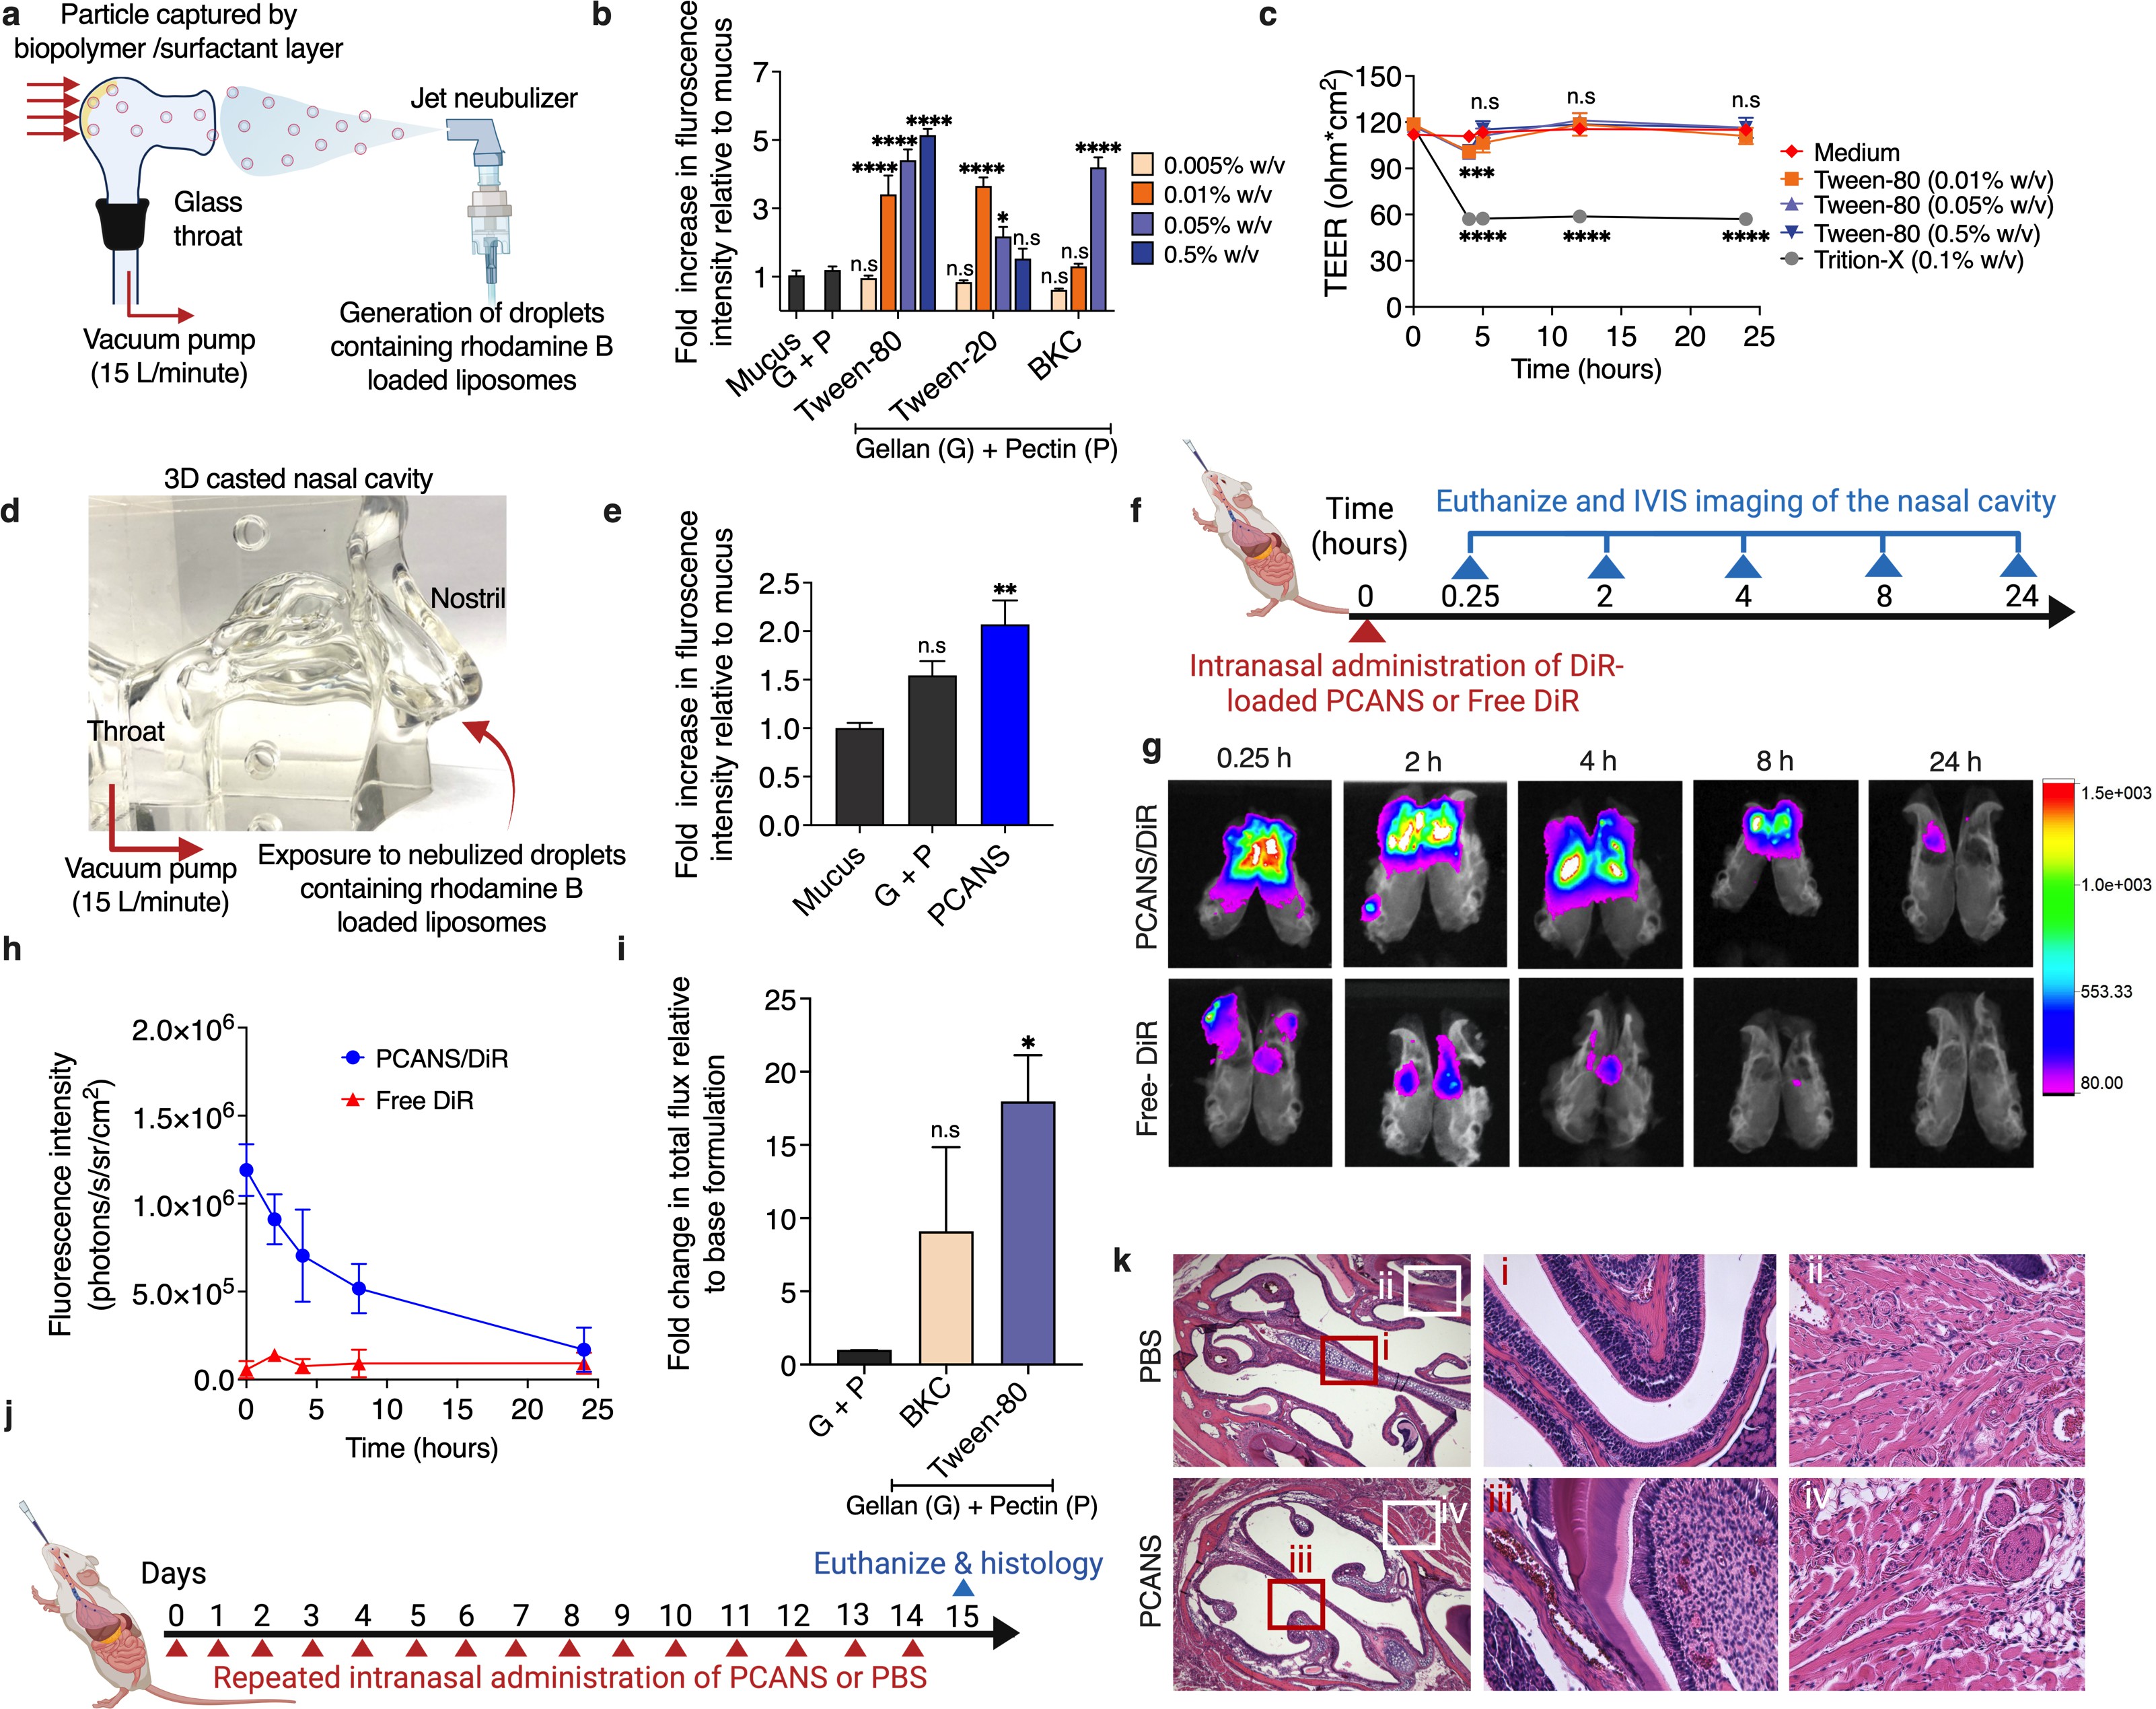
- untreated control. n.s, not significant. (d) Experimental design for measuring the capture of respiratory droplet-
- mimicking aerosol using a 3D human nasal cavity model (Koken cast). The inner surface of the nasal cavity
- was coated with mucus, G+P solution or PCANS (the final formulation) using a nasal spray device. The throat
- part of the model was coupled to a vacuum pump for simulating the respiratory airflow (15 L/min). Nostrils
- were then exposed to nebulized rhodamine B-loaded liposomes for 1 minute. Droplet capture was determined
- by quantifying the fluorescence intensity of rhodamine B in the nasal cavity. (e) Fold increase in fluorescence
- intensity with respect to mucus. **P < 0.01 compared to mucus. n.s, not significant. (f) Experimental outline for
- the evaluation of the nasal residence time of PCANS in mice. C57Bl/6 mice were intranasally administered with
- 10µL of free DiR or DiR-loaded PCANS (PCANS/DiR) into each nostril. Mice were euthanized at different time
- points over 24 h, and nasal cavity was harvested and imaged using an in vivo imaging system (IVIS). (g)
- Representative images of the nasal cavity excised at different time points. (h) Quantification of fluorescence
- intensity in the nasal cavity at different time points. (i) Fold change in total flux at 8h in the nasal cavity relative
- to G+P. *P < 0.05, compared to G+P. n.s, not significant. (i) Experimental design to assess the biocompatibility
- of PCANS in mouse nasal cavity. 10 µl PCANS or PBS was administered into each nostril of C57Bl/6 mice
- once daily for 14 consecutive days. Animals were euthanized on day 15 and nasal cavity was analyzed
- histologically. (j) Representative images of H&E-stained sections of nasal turbinate from mice captured using a
- 4X objective. Insets represent healthy olfactory epithelium (i) and (iii), and lamina propria (ii) and (iv) captured
- at 20X objective. For b, e and i, P values were determined by one-way ANOVA using Tukey’s post hoc
- analysis. For b, concentrations for each surfactant were compared individually. For c, P values were
- determined by two-way ANOVA with Tukey’s multiple comparison test. Data in b,c, and e are presented as
- Means ± S.D of biological repeats (n = 3, each experiment performed at least twice). Data in h and i are
- presented as Means ± SEM (n=5 mice/group).
Fig. 5: PCANS exhibits broad-spectrum physical barrier property with pathogen neutralization, and is
- sprayable and shelf-stable. (a-b) Amount of different viruses that permeated within 4 h through a simulated
- nasal fluid (SNF)-coated cell strainer or a cell strainer coated with simulated mucus/SNF mixture or PCANS/SNF
- mixture. Virus permeation was quantified by plaque assay in MDCK cells (IAV), Vero E6 cells (SARS-CoV-2),
- and Hep-2 cells (RSV and adenovirus) . ****P < 0.0001, ***P < 0.001, **P < 0.01, *P < 0.05. n.s, not significant.
- Amount of (e) E. coli and (f) K. pneumoniae that permeated within 4 h through an SNF-coated cell strainer or a
- cell strainer coated with simulated mucus/SNF mixture or PCANS/SNF mixture. Bacterial permeation was
- quantified using a CFU plate count method. ****P < 0.0001, ***P < 0.001, **P < 0.01. n.s, not significant. (g-k)
- Viral titer for IAV, SARS-CoV-2, adenovirus, and RSV after treatment with PBS or PCANS. IAV and SARS-CoV-
- 2 were incubated with PCANS for 10 min, while adenovirus and RSV were treated for 30 min. Anti-bacterial
- activity of PCANS against (k) E. coli and (l) Klebsiella pneumoniae using CFU plate count method after 30 and
- 10 min incubation, respectively. ***P < 0.001, **P < 0.01, *P < 0.05. (m) Spray characteristics of PCANS. The
- droplet size distribution of PCANS was analyzed using a laser diffraction system. Representative images of
- single time delay plume angle and ovality ratio, captured using a high-speed digital camera and laser light sheet.
- (n) Experimental design to assess the stability of PCANS in accelerated temperature conditions (40oC). PCANS
- was stored in glass amber bottles. Aliquots were taken at different time points to investigate spray characteristics
- and pathogen neutralization efficacy. (o) Plume angle, (p) ovality, (q) mean droplet diameter and (r) spray
- deposition area over a period of 60 days. ***P < 0.001, **P < 0.01 compared to day 0, n.s, not significant. (s)
- Percent reduction in the viral load of IAV and SARS-CoV-2 in their respective host cells after 10 min incubation
- with PCANS aliquoted at different time points in the stability study. *P < 0.05 compared to day 0. n.s, not
- significant. For a-f and o-s, P values were determined using one-way ANOVA with Tukey’s post-hoc analysis.
- For g-l, P values were determined using a two-tailed t-test. Data are presented as Means ± SD of biological
- repeats (n = 3, each experiment performed at least twice).
57
58
59
60
61
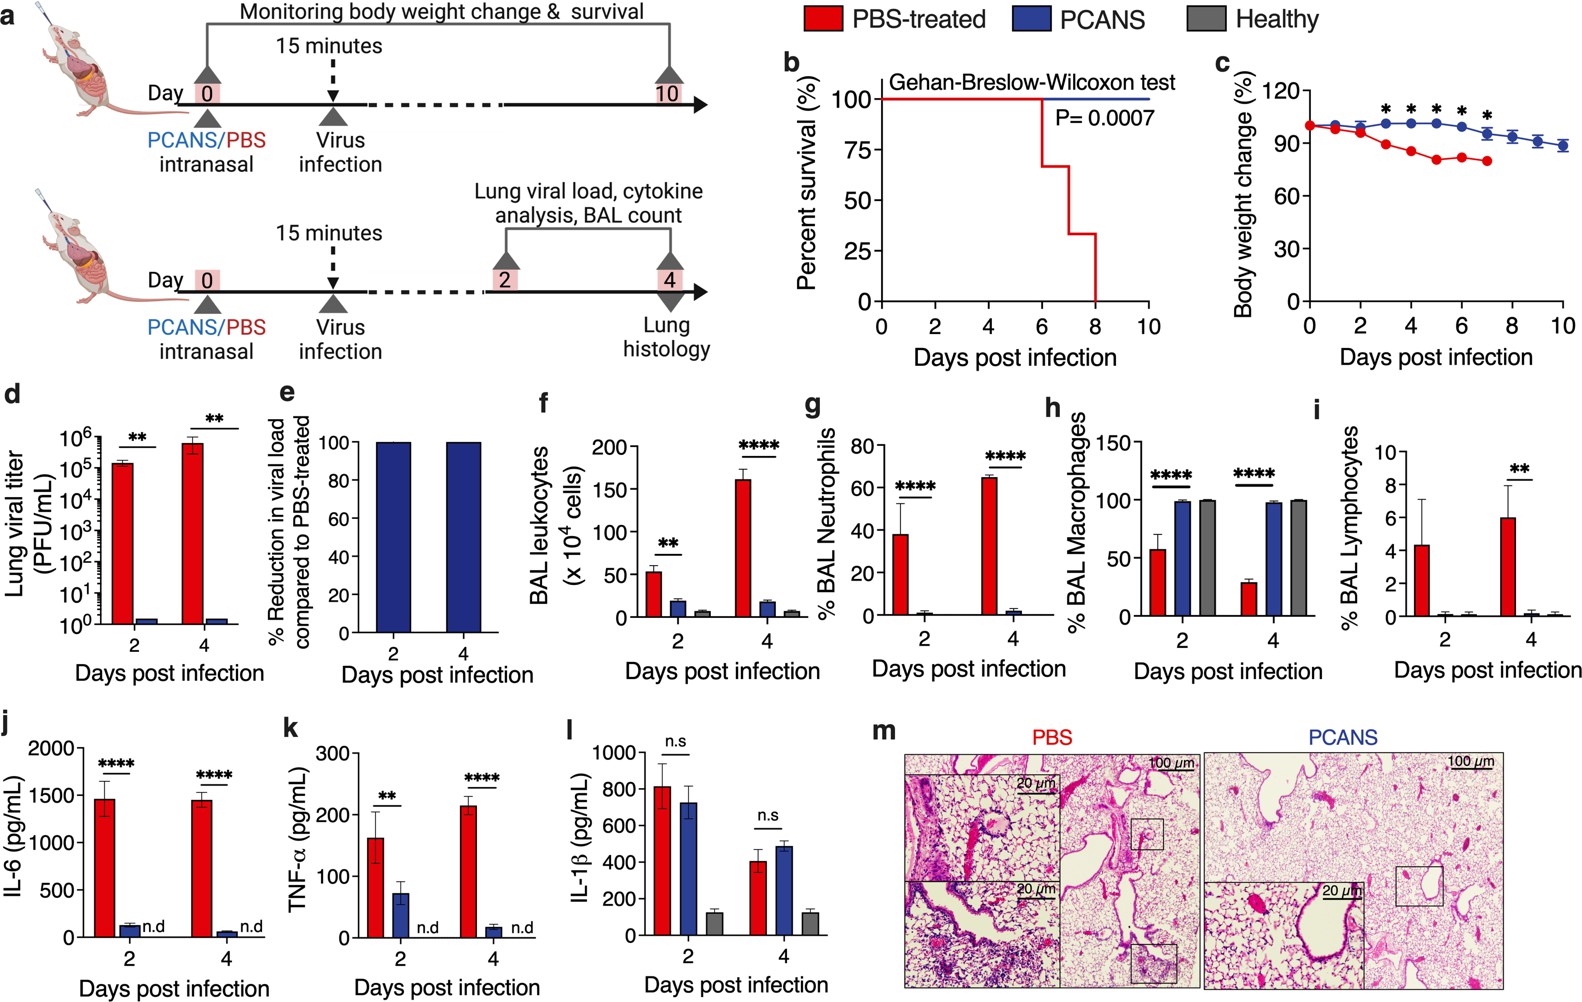
Fig. 6: Pre-exposure prophylactic treatment with intranasal PCANS reduces respiratory infection in mice.
- (a) Experimental outline for the prophylactic efficacy study. C57Bl/6 mice received a single dose (10 µl) of
- PCANS or PBS before 15 minutes of intranasal inoculation with 250 PFU Influenza A/PR/8/34. One cohort of
- animals was followed for body weight changes and survival for a period of 10 days. Animals from a second
- cohort were euthanized on day 2 or 4 after infection to enumerate lung viral titer, inflammatory cell count in
- bronchoalveolar lavage (BAL) fluid, and inflammatory cytokine levels in lung homogenate. Hematoxylin and
- eosin (H&E) stained lung tissue sections from animals euthanized were assessed for inflammation. (b) Survival
- and (c) body weight change of mice over a period of 10 days post-infection. P = 0.0007 compared to the PBS-
- treated group for Kaplan-Meier survival curve. * P < 0.01 compared to PBS-treated group for body weight change
- curves. (d) Viral titer from lung homogenate of mice and (e) percentage reduction in viral load in the lungs on
- day 2 and 4 post-infection, as quantified by plaque assay performed in MDCK cells. **P = 0.001. (f-i)
- Inflammatory cell count in BAL on day 2 and 4 after infection. ****P < 0.0001, **P < 0.01. Levels of (j) IL-6, (k)
- TNF- α and (l) IL-1β in lung tissues. ****P < 0.0001, **P = 0.005. n.s, non-significant, n.d, not detected. (m)
- Representative images of H&E-stained lung tissue sections of virus-challenged mice that were prophylactically
- treated with PBS or PCANS. Histology images were captured using 10X and 40X objectives. Scale bar: 100 µm.
- High-magnified insets depict the difference in the extent of inflammatory infiltrates. Scale bar: 20 µm. For b, P
- values were determined using the Gehan-Breslow-Wilcoxon test. For c, P values were determined using one-
- way ANOVA with Brown-Forsythe. For d and f-l, P values were determined using two-way ANOVA with Tukey’s
- post hoc analysis. For o, P values were determined using one-way ANOVA with Tukey’s post hoc analysis. n=6
- mice/group for b. Data in c are presented as Means ± SEM (n=6 mice/group). Data in d-l are presented as
- Means ± SEM (n=4 mice/group).
84
85
86
87