
Summary
Nasal irrigation, especially with undiluted seawater, is highly effective for treating various nasal conditions and improving overall nasal health.
Key points
- Nasal irrigation is effective for treating sinonasal issues.
- Large-volume low-pressure irrigation with undiluted seawater is the most effective method.
- Seawater has beneficial components like bicarbonates, potassium, calcium, and magnesium.
- Slightly alkaline pH enhances mucociliary function.
- No single irrigation solution is proven superior; further studies are needed.
Notes
“Large-volume low-pressure nasal irrigation using undiluted seawater seems, in the present state of knowledge, to be the most effective protocol.”
Outline
Abstract
Nasal irrigation (opens in a new tab) plays a non-negligible role in the treatment of numerous sinonasal pathologies and postoperative care. There is, however, a wide variety of protocols. The present review of the evidence-based literature sought objective arguments for optimization and efficacy. It emerged that large-volume low-pressure nasal douche optimizes the distribution and cleansing power of the irrigation solution (opens in a new tab) in the nasal cavity (opens in a new tab). Ionic composition and pH also influence mucociliary clearance (opens in a new tab) and epithelium trophicity. Seawater is less rich in sodium ions and richer in bicarbonates, potassium, calcium and magnesium than is isotonic normal saline, while alkaline pH and elevated calcium concentration optimized ciliary motility (opens in a new tab) in vitro. Bicarbonates (opens in a new tab) reduce secretion viscosity. Potassium and magnesium promote healing and limit local inflammation. These results show that the efficacy of nasal irrigation is multifactorial. Large-volume low-pressure nasal irrigation using undiluted seawater seems, in the present state of knowledge, to be the most effective protocol.
Keywords
Nasal irrigation
Seawater
Saline solution
1. Introduction
Several national and international consensus conferences now recommend nasal irrigation (opens in a new tab) as adjuvant treatment in numerous sinonasal pathologies [1] (opens in a new tab), [2] (opens in a new tab), [3] (opens in a new tab), [4] (opens in a new tab), [5] (opens in a new tab), [6] (opens in a new tab). It provides mechanical cleansing of mucus (opens in a new tab), crust, cell debris and various air contaminants (pathogens, allergens, airborne particles, etc.). It enhances mucociliary clearance (opens in a new tab) [7] (opens in a new tab), [8] (opens in a new tab) and reduces the mucus contact time of airborne elements. It reduces local concentrations of pro-inflammatory mediators [9] (opens in a new tab), [10] (opens in a new tab), [11] (opens in a new tab) and humidifies the nasal mucosa (opens in a new tab), notably postoperatively and in many chronic sinonasal pathologies.
A recent meta-analysis of 10 controlled trials taken from a review of 11,500 studies included more than 400 allergic rhinitis (opens in a new tab) patients [7] (opens in a new tab). Regular saline irrigation in adults and children improved nasal symptomatology (opens in a new tab) in 35% of cases and quality of life in 30%. Mucociliary clearance on saccharine (opens in a new tab) test was increased by about 30%. The impact on medical drug consumption was harder to quantify; moreover, the included population was small for such a common treatment, and methods and administration times varied greatly, limiting the scientific value of the study [7] (opens in a new tab).
The heterogeneity of the literature makes it difficult to get any clear idea concerning the various solutions and means of administration. Irrigation solution (opens in a new tab) composition would seem to be an important issue: chronic patients sometimes report improvement with sea bathing, and some studies suggest that irrigation solutions taken from certain seas provide better functional improvement [12] (opens in a new tab), [13] (opens in a new tab).
The present article comprises a literature review and update on the various solutions and means of administration available.
1.1. Means of irrigation
To the best of our knowledge, there is no consensus regarding means of irrigation. A study of the cavity distribution of 40 mL of radio-opaque substance in healthy subjects reported benefit with positive pressure irrigation versus negative pressure administration (by sniffing) or nebulization: nasal cavity (opens in a new tab) and sinus distribution was more exhaustive [14] (opens in a new tab). Wormald et al., using 5 mL Tc99m-labeled irrigation solution, found better nasal cavity and sinus distribution with douche administration than nebulization or sprays [15] (opens in a new tab).
We found no studies, comparative or not, in the literature focusing on syringe administration, despite this being the most widespread method. Several studies reported greater efficacy with large-volume irrigation [16] (opens in a new tab), [17] (opens in a new tab). A recent study compared 26 nasal irrigation devices available on the German market [18] (opens in a new tab), testing them on a resin nasal cavity model based on normal non-congested cadaver nostrils. Irrigation volumes ranged from 30 to 500 mL, for a mean 200–250 mL. The greater the irrigation volume, the larger the cavity area covered by the irrigation: large-volume irrigation reaches a larger proportion of the nasal cavities. Depending on volume and device, application time ranged between 6 and 54 s, and output between 3.9 and 27.2 mL/s. Only compression systems delivering ≥120 mbar pressure reached the entire nasal cavity. The authors added that tight fit between nozzle and nostril and the possibility of inserting the nozzle into the vestibule (opens in a new tab) and orienting it 45° upward optimized cavity coverage and minimized loss of irrigation solution [18] (opens in a new tab). It also appeared that good ergonomics, irrigation quality and microbial safety were associated with devices that were transparent, equipped with an anti-reflux nozzle, in high-quality supple and compressible plastic, with ≥5 mL/s output or ≥120 mbar administration pressure, that could be taken apart and washed by hand or in a dishwasher, and were adapted for microwave ovens.
Clinically, a prospective single-blind randomized study compared postoperative efficacy between two commercially available nasal irrigation devices; in 31 endonasal surgery patients, large-volume low-pressure irrigation was associated with better postoperative nasal cavity cleansing on the Lund-Mackay postoperative endoscopy (opens in a new tab) score than low-volume high-pressure irrigation [19] (opens in a new tab).
1.2. In vitro data
1.2.1. Composition of commercially available solutions
It is important to be aware of the fact that the exact composition of the various products and recipes could not be found in the literature, except for Physiomer®1 (opens in a new tab) and Ringer's lactate (opens in a new tab). Table 1 (opens in a new tab) and Fig. 1 (opens in a new tab) show the chemical compositions of the various nasal irrigation solutions. There are several “recipes” for “home-made” saline, with or without buffer, that patients can make up themselves at home, using water, salt and, in some cases, sodium bicarbonate (opens in a new tab). Unlike normal saline (NaCl 0.9%), composition and sterility are neither controllable, reproducible or reliable. Home-made solutions using “sea” salt contain only chloride ions (opens in a new tab) and sodium.
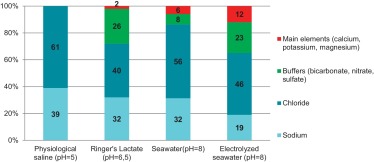
Fig. 1. Physical and chemical characteristics of various isotonic saline solutions versus seawater (biochemical analyses provided by Laboratoire de la Mer®).
Download : Download full-size image
There are also commercially available products consisting of seawater diluted to one-third in distilled water (e.g., Stérimar®2 (opens in a new tab), Marimer®3 (opens in a new tab), Vicks®4 (opens in a new tab)) to obtain an isotonic solution (opens in a new tab). Although these are marketed as “seawater”, the one-third dilution conserves only part of the naturally present minerals, which are themselves proportionally diluted (http://www.sterimar.com/en/nasal-family-solutions.php (opens in a new tab)). Another product consists of electrodialyzed seawater (Physiomer®), providing an isotonic solution with reliable osmolarity, while conserving high concentrations of the main seawater ions (https://register.epo.org/application?lng=en&number=EP98460042 (opens in a new tab)). Its composition is known and can be compared to physiological saline and Ringer's lactate (Table 1 (opens in a new tab)). Products obtained by this procedure are, like Ringer's lactate, rich in calcium, potassium and magnesium ions (opens in a new tab) and buffering (bicarbonates), with low sodium ion content (Table 1 (opens in a new tab)). Like seawater, they have slightly alkaline pH (controlled pH close to 8), while normal saline is acidic, with pH varying from 4.5 to 7.
1.2.2. Role of the various components
It is now agreed that, in vitro, these ions show non-negligible action on epithelial cells. Sodium ions can inhibit hair-cell calcium flow, thus reducing ciliary beat frequency [20] (opens in a new tab). Magnesium ions reduce local inflammation by reducing mediator secretion [21] (opens in a new tab) and degranulation (opens in a new tab) [22] (opens in a new tab) in cells implicated in allergy. Paradoxically, they increase IL-8 secretion by nasal epithelial cells [23] (opens in a new tab). Finally, magnesium and zinc can reduce respiratory mucosa cell (opens in a new tab) apoptosis (opens in a new tab) during inflammatory processes [24] (opens in a new tab). Calcium is involved in regulating ciliary beat frequency and synchronization, via various ciliated cell surface receptors (opens in a new tab) [25] (opens in a new tab), in all of which acetylcholine (opens in a new tab) and serotonin act as messengers by increasing cell calcium intake (opens in a new tab) [25] (opens in a new tab). Airflow also stimulates cell calcium intake and ciliary beat via shear-stress-induced mechanotransduction (opens in a new tab) [25] (opens in a new tab). Potassium promotes respiratory epithelium (opens in a new tab) repair via the EGF/EGFR pathway [26] (opens in a new tab), [27] (opens in a new tab). Bicarbonate ions, as well as acting as buffer, efficiently reduce mucus viscosity, thus facilitating elimination by ciliated cell movement [28] (opens in a new tab).
1.2.3. Role of pH and tonicity
In vitro, solutions with pH <7 or >10 reduced tracheal mucosa (opens in a new tab) ciliary beat frequency in rats and chicken embryos [29] (opens in a new tab). In humans, solutions with acidic pH likewise reduced ciliary beat frequency, while slightly alkaline solutions enhanced it [30] (opens in a new tab), [31] (opens in a new tab). In vivo, on the other hand, in humans, pH impact on mucociliary clearance is more difficult to ascertain. England et al. found no statistical correlation between pH and mucociliary clearance in 56 healthy non-smokers [32] (opens in a new tab). More recently, Chusakul et al. reported clear improvement in symptoms with alkaline isotonic solutions in allergic rhinitis; mucociliary clearance, on the other hand, was unaffected whatever the pH, in a range from 6.2 to 8.4 [33] (opens in a new tab). However, change in mucociliary clearance seems not to depend exclusively on pH: in vitro, in chicken embryo tracheal explants, hypertonic (1.5%) and hypotonic (0.45%) irrigation both reduced ciliary beat frequency as compared to physiological (0.9%) saline [29] (opens in a new tab). Beat arrest was irreversible with a 14% solution, and hypertonicity (opens in a new tab) triggered mucus hypersecretion and increased the permeability of tight junctions [34] (opens in a new tab), [35] (opens in a new tab), [36] (opens in a new tab). These data correlated in vivo with increased secretion and exudation in response to hypertonic solutions [37] (opens in a new tab). Paradoxically, other authors reported improved in vivo mucociliary clearance on saccharine test in healthy subjects with hypertonic solutions between 3% and 5% [38] (opens in a new tab), [39] (opens in a new tab).
1.2.4. Advantages of seawater
Since 1995, it has been shown that seawater promotes cell growth, with a significantly stronger eutrophic effect than normal saline or seawater at one-third dilution [40] (opens in a new tab). In a more recent in vitro study, 2 to 4 hours’ exposure to electrodialyzed seawater enhanced viability in deprived bronchial epithelial cells as compared to isotonic normal saline [11] (opens in a new tab). In other studies, seawater significantly protected pig nasal mucosa against the effects of twice-daily 0.1% oxymetazoline (opens in a new tab) (inflammation, fibrosis, metaplasia) [41] (opens in a new tab).
In vitro, electrodialyzed seawater reduced production of pro-inflammatory molecules such as IL-8 or RANTES (opens in a new tab) [10] (opens in a new tab), [11] (opens in a new tab), involved in the recruitment and activation of polynuclear neutrophils (opens in a new tab) and eosinophils (opens in a new tab).
Thus, in vitro at least, it would seem that limited sodium chloride content is important for nasal irrigation solutions. Conversely, calcium provides an advantage in terms of restoring epithelial trophicity and mucociliary efficacy. Potassium should provide benefit in postoperative situations and/or certain chronic rhinosinusitis (opens in a new tab) via its action on anti-inflammatory response; slightly alkaline pH with isotonic composition should have a similar effect.
1.3. Clinical advantages of undiluted seawater over other irrigation solutions
Certain studies reported clinical superiority for mineral-rich solutions compared to classic saline, but data are sparse (Table 2 (opens in a new tab)).
- Statistical significative difference; nk: not known. In allergic rhinitis, iso- and hypertonic saline improved all symptoms in children, reducing recourse to antihistamines (opens in a new tab) and corticosteroids [42] (opens in a new tab), [43] (opens in a new tab), with excellent tolerance [44] (opens in a new tab), [45] (opens in a new tab). In 2007, a multicenter randomized study assessed the efficacy of electrodialyzed 2.2% hypertonic Saint-Malo seawater in 238 allergic or non-allergic chronic rhinosinusitis patients, and found strongly significantly superiority for nasal irrigation (with or without local corticosteroids) versus controls (antihistamines with local corticosteroids, without irrigation) in terms of symptoms and of recourse to corticosteroids [46] (opens in a new tab). Cordray et al. likewise reported that nasal irrigation with water from the Dead Sea, without antihistamines, was as effective as local corticosteroids in controlling nasal and ocular symptoms in mild-to-moderate seasonal allergic rhinitis (opens in a new tab) [12] (opens in a new tab). Friedman et al., in a prospective randomized double-blind study, found greater improvement in symptom scores in 42 allergic or non-allergic chronic rhinosinusitis patients with Dead Sea water versus hypertonic saline [13] (opens in a new tab). The same author, using the same methodology, more recently reported a similar improvement in symptoms in 114 patients with irrigation with hypertonic Dead Sea water without corticotherapy (opens in a new tab) versus hypertonic saline with local corticosteroids [47] (opens in a new tab).
In acute infection, two prospective randomized studies showed better treatment with nasal irrigation. The first, a controlled multicenter study of 390 children with rhinitis, found faster improvement in nasal permeability and the quality and quantity of secretion with electrodialyzed seawater irrigation than in a control group without irrigation [48] (opens in a new tab). It also demonstrated that irrigation reduced number of episodes, ENT complications and medication (antipyretics, antibiotics, mucolytics (opens in a new tab) and decongestants) in children suffering from frequent rhinitis [48] (opens in a new tab). The second, single-center, study of 69 children with acute sinusitis (opens in a new tab), found that standard treatment (antibiotics, mucolytics and local nasal decongestants) reduced symptoms more effectively when associated to nasal irrigation with an isotonic solution [49] (opens in a new tab). Both studies showed the efficacy of irrigation in these respective pathologies, but did not demonstrate the superiority of either solution, as there was no comparative arm.
In postoperative use, nasal irrigation is essential for cleansing the crusts and secretions inherent to any sinonasal surgery. It significantly reduces nasal secretion (opens in a new tab) and shows a tendency to reduce postsurgical edema. Ringer's lactate, which is rich in calcium and potassium and less rich in sodium and chloride ions than isotonic saline, provided a stronger increase in mucociliary transport (opens in a new tab) than isotonic saline after endonasal surgery [50] (opens in a new tab).
Few studies have focused on postoperative seawater irrigation [51] (opens in a new tab), [52] (opens in a new tab), [53] (opens in a new tab), and they lacked control groups without postoperative care to remove clots, crusts and secretion. Pigret and Jankowski found no significant difference between the effects of pressurized seawater and saline with antiseptics and mucolytics, in a small series (10 patients per group) [51] (opens in a new tab). Keerl et al., in an observational study of 121 patients, found nasal irrigation to be well tolerated, and that some patients continued in the long-term, including irrigation in their daily life routine [52] (opens in a new tab). Pinto et al. found no symptomatic benefit of irrigation, whether iso- or hypertonic [53] (opens in a new tab), and recommended not implementing postoperative irrigation; their study, however involved certain defects: no inclusion criteria, and no details of surgical technique, numerous revision surgeries and application of an endonasal hemostasis (opens in a new tab) substance. Moreover, the symptoms scores used were not validated, and final nasal cavity status was not noted [53] (opens in a new tab).
Finally, certain preservatives, antiseptics and mucolytics have sometimes been associated to irrigation solutions. They slowed or arrested ciliary beat, and showed no clinical benefit [51] (opens in a new tab), [54] (opens in a new tab), [55] (opens in a new tab). A recent meta-analysis confirmed the non-superiority of adding an antibiotic and an antifungal (opens in a new tab) agent to the irrigation solution in chronic rhinosinusitis [6] (opens in a new tab).
2. Conclusion
Founded on empirical practice and common sense, nasal irrigation (opens in a new tab) now plays an essential and self-evident role for the large majority of practitioners. The heterogeneity of protocols and studies make for confusion. It would, however, appear that: large-volume irrigation provides good distribution over the sinonasal cavities as a whole; and a stable, reproducible isotonic solution (opens in a new tab) with slightly alkaline pH and a composition close to that of seawater optimizes trophic and functional recovery of the respiratory epithelium (opens in a new tab). Clinically, the literature fails to prove any clear superiority of one product over the others; however, the in vitro properties of undiluted seawater seem to provide definite advantage in many clinical situations, as compared with physiological saline. Further studies will be needed to confirm the present findings.
Disclosure of interest
L. de Gabory: occasional expert reports, consultancy and guest speaker for Laboratoire de la Mer®.
The other authors declare that they have no conflicts of interest concerning this article.
Acknowledgments
The authors thank Laboratoire de la Mer® for the data for the composition of the irrigation solutions shown in Fig. 1 (opens in a new tab).
References
[1] (opens in a new tab)Société française d’oto-rhino-laryngologieRecommandation pour la pratique clinique : les thérapeutiques périopératoires en chirurgie endonasale (2001)[accessed November 21, 2013]http://www.orlfrance.org/download.php?id=61 (opens in a new tab)Google Scholar (opens in a new tab)[2] (opens in a new tab)D. Price, C. Bond, J. Bouchard, R. Costa, J. Keenan, M.L. Levy, * et al.*International Primary Care Respiratory Group (IPCRG) guidelines: management of allergic rhinitis**Prim Care Respir J, 15 (2006), pp. 58-70Article (opens in a new tab)Download PDF (opens in a new tab)CrossRef (opens in a new tab)View Record in Scopus (opens in a new tab)Google Scholar (opens in a new tab)[3] (opens in a new tab)R.M. Rosenfeld, D. Andes, N. Bhattacharyya, D. Cheung, S. Eisenberg, T.G. Ganiats, * et al.***Clinical practice guideline: adult sinusitis**Otolaryngol Head Neck Surg, 137 (2007), pp. S1-S31Article (opens in a new tab)Download PDF (opens in a new tab)View Record in Scopus (opens in a new tab)Google Scholar (opens in a new tab)[4] (opens in a new tab)R. Harvey, S.A. Hannan, L. Badia, G. ScaddingNasal saline irrigations for the symptoms of chronic rhinosinusitis*Cochrane Database Syst Rev (2007), p. CD006394View Record in Scopus (opens in a new tab)Google Scholar (opens in a new tab)[5] (opens in a new tab)W.J. Fokkens, V.J. Lund, J. Mullol, C. Bachert, I. Alobid, F. Baroody, * et al.EPOS 2012: European position paper on rhinosinusitis and nasal polyps 2012. A summary for otorhinolaryngologistsRhinology, 50 (2012), pp. 1-12View Record in Scopus (opens in a new tab)Google Scholar (opens in a new tab)[6] (opens in a new tab)C.C. Wei, N.D. Adappa, N.A. Cohen*Use of topical nasal therapies in the management of chronic rhinosinusitis*Laryngoscope, 123 (2013), pp. 2347-2359CrossRef (opens in a new tab)View Record in Scopus (opens in a new tab)Google Scholar (opens in a new tab)[7] (opens in a new tab)K.E. Hermelingmeier, R.K. Weber, M. Hellmich, C.P. Heubach, R. MösgesNasal irrigation as an adjunctive treatment in allergic rhinitis: a systematic review and meta-analysisAm J Rhinol Allergy, 26 (2012), pp. e119-e125CrossRef (opens in a new tab)View Record in Scopus (opens in a new tab)Google Scholar (opens in a new tab)[8] (opens in a new tab)A. Satdhabudha, O. PoachanukoonEfficacy of buffered hypertonic saline nasal irrigation in children with symptomatic allergic rhinitis: a randomized double-blind studyInt J Pediatr Otorhinolaryngol, 76 (2012), pp. 583-588Article (opens in a new tab)Download PDF (opens in a new tab)View Record in Scopus (opens in a new tab)Google Scholar (opens in a new tab)[9] (opens in a new tab)J.W. GeorgitisNasal hyperthermia and simple irrigation for perennial rhinitis. Changes in inflammatory mediatorsChest, 106 (1994), pp. 1487-1492Article (opens in a new tab)Download PDF (opens in a new tab)CrossRef (opens in a new tab)View Record in Scopus (opens in a new tab)Google Scholar (opens in a new tab)[10] (opens in a new tab)O. Tabary, C. Muselet, J.C. Yvin, B. Halley-Vanhove, E. Puchelle, J. JacquotPhysiomer reduces the chemokine interleukin-8 production by activated human respiratory epithelial cellsEur Respir J, 18 (2001), pp. 661-666View Record in Scopus (opens in a new tab)Google Scholar (opens in a new tab)[11] (opens in a new tab)O. Tabary, C. Muselet, M.C. Miesch, J.C. Yvin, A. Clément, J. JacquotReduction of chemokine IL-8 and RANTES expression in human bronchial epithelial cells by a sea-water derived saline through inhibited nuclear factor-kappaB activationBiochem Biophys Res Commun, 309 (2003), pp. 310-316Article (opens in a new tab)Download PDF (opens in a new tab)View Record in Scopus (opens in a new tab)Google Scholar (opens in a new tab)[12] (opens in a new tab)S. Cordray, J.B. Harjo, L. MinerComparison of intranasal hypertonic dead sea saline spray and intranasal aqueous triamcinolone spray in seasonal allergic rhinitisEar Nose Throat J, 84 (2005), pp. 426-430CrossRef (opens in a new tab)View Record in Scopus (opens in a new tab)Google Scholar (opens in a new tab)[13] (opens in a new tab)M. Friedman, R. Vidyasagar, N. JosephA randomized, prospective, double-blind study on the efficacy of dead sea salt nasal irrigationsLaryngoscope, 116 (2006), pp. 878-882CrossRef (opens in a new tab)View Record in Scopus (opens in a new tab)Google Scholar (opens in a new tab)[14] (opens in a new tab)D.E.L. Olson, B.M. Rasgon, R.L. Hilsinger Jr.Radiographic comparison of three methods for nasal saline irrigationLaryngoscope, 112 (2002), pp. 1394-1398View Record in Scopus (opens in a new tab)Google Scholar (opens in a new tab)[15] (opens in a new tab)P.-J. Wormald, T. Cain, L. Oates, L. Hawke, I. WongA comparative study of three methods of nasal irrigationLaryngoscope, 114 (2004), pp. 2224-2227CrossRef (opens in a new tab)View Record in Scopus (opens in a new tab)Google Scholar (opens in a new tab)[16] (opens in a new tab)M.A. Pynnonen, S.S. Mukerji, H.M. Kim, M.E. Adams, J.E. TerrellNasal saline for chronic sinonasal symptoms: a randomized controlled trialArch Otolaryngol Head Neck Surg, 133 (2007), pp. 1115-1120CrossRef (opens in a new tab)View Record in Scopus (opens in a new tab)Google Scholar (opens in a new tab)[17] (opens in a new tab)R.J. Harvey, J.C. Goddard, S.K. Wise, R.J. SchlosserEffects of endoscopic sinus surgery and delivery device on cadaver sinus irrigationOtolaryngol Head Neck Surg, 139 (2008), pp. 137-142Article (opens in a new tab)Download PDF (opens in a new tab)CrossRef (opens in a new tab)View Record in Scopus (opens in a new tab)Google Scholar (opens in a new tab)[18] (opens in a new tab)J. Campos, W. Heppt, R. WeberNasal douches for diseases of the nose and the paranasal sinuses – a comparative in vitro investigationEur Arch Otorhinolaryngol, 270 (2013), pp. 2891-2899CrossRef (opens in a new tab)View Record in Scopus (opens in a new tab)Google Scholar (opens in a new tab)[19] (opens in a new tab)R.J. Salib, S. Talpallikar, S. Uppal, S.B. NairA prospective randomised single-blinded clinical trial comparing the efficacy and tolerability of the nasal douching products Sterimar™ and Sinus Rinse™ following functional endoscopic sinus surgeryClin Otolaryngol, 38 (2013), pp. 297-305, 10.1111/coa.12132 (opens in a new tab)View Record in Scopus (opens in a new tab)Google Scholar (opens in a new tab)[20] (opens in a new tab)W. Ma, A. Korngreen, N. Uzlaner, Z. Priel, S.D. SilberbergExtracellular sodium regulates airway ciliary motility by inhibiting a P2X receptorNature, 400 (1999), pp. 894-897View Record in Scopus (opens in a new tab)Google Scholar (opens in a new tab)[21] (opens in a new tab)P. Ludwig, K. Petrich, T. Schewe, W. DiezelInhibition of eicosanoid formation in human polymorphonuclear leukocytes by high concentrations of magnesium ionsBiol Chem, 376 (1995), pp. 739-744CrossRef (opens in a new tab)View Record in Scopus (opens in a new tab)Google Scholar (opens in a new tab)[22] (opens in a new tab)K.Y. Larbi, B.D. GompertsComplex pattern of inhibition by Mg2+ of exocytosis from permeabilised eosinophilsCell Calcium, 21 (1997), pp. 213-219Article (opens in a new tab)Download PDF (opens in a new tab)View Record in Scopus (opens in a new tab)Google Scholar (opens in a new tab)[23] (opens in a new tab)S. Schumacher, I. Roth, J. Stahl, W. Bäumer, M. KietzmannBiodegradation of metallic magnesium elicits an inflammatory response in primary nasal epithelial cellsActa Biomater, 10 (2014), pp. 996-1004Article (opens in a new tab)Download PDF (opens in a new tab)View Record in Scopus (opens in a new tab)Google Scholar (opens in a new tab)[24] (opens in a new tab)Y. TesfaigziRoles of apoptosis in airway epitheliaAm J Respir Cell Mol Biol, 34 (2006), pp. 537-547View Record in Scopus (opens in a new tab)Google Scholar (opens in a new tab)[25] (opens in a new tab)A. Schmid, M. SalatheCiliary beat co-ordination by calciumBiol Cell, 103 (2011), pp. 159-169View Record in Scopus (opens in a new tab)Google Scholar (opens in a new tab)[26] (opens in a new tab)N.T.N. Trinh, A. Privé, E. Maillé, J. Noël, E. BrochieroEGF and K+ channel activity control normal and cystic fibrosis bronchial epithelia repairAm J Physiol Lung Cell Mol Physiol, 295 (2008), pp. L866-L880CrossRef (opens in a new tab)View Record in Scopus (opens in a new tab)Google Scholar (opens in a new tab)[27] (opens in a new tab)P.J. Buchanan, P. McNally, B.J. Harvey, V. UrbachLipoxin A4-mediated KATP potassium channel activation results in cystic fibrosis airway epithelial repairAm J Physiol Lung Cell Mol Physiol, 305 (2013), pp. L193-L201CrossRef (opens in a new tab)View Record in Scopus (opens in a new tab)Google Scholar (opens in a new tab)[28] (opens in a new tab)E.Y.T. Chen, N. Yang, P.M. Quinton, W.-C. ChinA new role for bicarbonate in mucus formationAm J Physiol Lung Cell Mol Physiol, 299 (2010), pp. L542-L549CrossRef (opens in a new tab)View Record in Scopus (opens in a new tab)Google Scholar (opens in a new tab)[29] (opens in a new tab)H.J. Van de Donk, J. Zuidema, F.W. MerkusThe influence of the pH and osmotic pressure upon tracheal ciliary beat frequency as determined with a new photo-electric registration deviceRhinology, 18 (1980), pp. 93-104View Record in Scopus (opens in a new tab)Google Scholar (opens in a new tab)[30] (opens in a new tab)C.K. Luk, M.J. DulfanoEffect of pH, viscosity and ionic-strength changes on ciliary beating frequency of human bronchial explantsClin Sci (Lond), 64 (1983), pp. 449-451CrossRef (opens in a new tab)View Record in Scopus (opens in a new tab)Google Scholar (opens in a new tab)[31] (opens in a new tab)A. Zsembery, A.T. Boyce, L. Liang, J. Peti-Peterdi, P.D. Bell, E.M. SchwiebertSustained calcium entry through P2X nucleotide receptor channels in human airway epithelial cellsJ Biol Chem, 278 (2003), pp. 13398-13408Article (opens in a new tab)Download PDF (opens in a new tab)View Record in Scopus (opens in a new tab)Google Scholar (opens in a new tab)[32] (opens in a new tab)R.J. England, R. Anthony, J.J. Homer, D.P. Martin-HirschNasal pH and saccharin clearance are unrelated in the physiologically normal noseRhinology, 38 (2000), pp. 66-67View Record in Scopus (opens in a new tab)Google Scholar (opens in a new tab)[33] (opens in a new tab)S. Chusakul, S. Warathanasin, N. Suksangpanya, C. Phannaso, S. Ruxrungtham, K. Snidvongs, * et al.Comparison of buffered and nonbuffered nasal saline irrigations in treating allergic rhinitisLaryngoscope, 123 (2013), pp. 53-56, 10.1002/lary.23617 (opens in a new tab)View Record in Scopus (opens in a new tab)Google Scholar (opens in a new tab)[34] (opens in a new tab)W.M. Boek, N. Keleş, K. Graamans, E.H. Huizing*Physiologic and hypertonic saline solutions impair ciliary activity in vitroLaryngoscope, 109 (1999), pp. 396-399View Record in Scopus (opens in a new tab)Google Scholar (opens in a new tab)[35] (opens in a new tab)T.M. Dwyer, J.M. FarleyMucus glycoconjugate secretion in cool and hypertonic solutionsAm J Physiol, 272 (1997), pp. L1121-L1125CrossRef (opens in a new tab)View Record in Scopus (opens in a new tab)Google Scholar (opens in a new tab)[36] (opens in a new tab)M. Högman, A.C. Mörk, G.M. RoomansHypertonic saline increases tight junction permeability in airway epitheliumEur Respir J, 20 (2002), pp. 1444-1448View Record in Scopus (opens in a new tab)Google Scholar (opens in a new tab)[37] (opens in a new tab)L. Greiff, M. Andersson, P. Wollmer, C.G.A. PerssonHypertonic saline increases secretory and exudative responsiveness of human nasal airway in vivoEur Respir J, 21 (2003), pp. 308-312View Record in Scopus (opens in a new tab)Google Scholar (opens in a new tab)[38] (opens in a new tab)A.R. Talbot, T.M. Herr, D.S. ParsonsMucociliary clearance and buffered hypertonic saline solutionLaryngoscope, 107 (1997), pp. 500-503View Record in Scopus (opens in a new tab)Google Scholar (opens in a new tab)[39] (opens in a new tab)J.J. Homer, A.C. Dowley, L. Condon, P. El-Jassar, S. SoodThe effect of hypertonicity on nasal mucociliary clearanceClin Otolaryngol Allied Sci, 25 (2000), pp. 558-560View Record in Scopus (opens in a new tab)Google Scholar (opens in a new tab)[40] (opens in a new tab)L. Traissac, L. Bordenave, R. Bareille, C. Bacquey, C. CourtesÉtude in vitro de l’action des dérivés de l’eau de mer sur la muqueuse respiratoire*Rev Off Soc Fr ORL, 32 (1995), pp. 43-49View Record in Scopus (opens in a new tab)Google Scholar (opens in a new tab)[41] (opens in a new tab)E. Nikolaidis, A. Eleftheriadou, I. Yiotakis, A.C. Lazaris, G. Agrogianis, E. Ferekidou, * et al.Influence of intranasal sterile isotonic sea water applications on xylometazoline administration: an experimental study in pigsAuris Nasus Larynx, 37 (2010), pp. 71-76Article (opens in a new tab)Download PDF (opens in a new tab)View Record in Scopus (opens in a new tab)Google Scholar (opens in a new tab)[42] (opens in a new tab)W. Garavello, M. Romagnoli, L. Sordo, R.M. Gaini, C. Di Berardino, A. Angrisano*Hypersaline nasal irrigation in children with symptomatic seasonal allergic rhinitis: a randomized study*Pediatr Allergy Immunol, 14 (2003), pp. 140-143CrossRef (opens in a new tab)View Record in Scopus (opens in a new tab)Google Scholar (opens in a new tab)[43] (opens in a new tab)H. Li, Q. Sha, K. Zuo, H. Jiang, L. Cheng, J. Shi, * et al.Nasal saline irrigation facilitates control of allergic rhinitis by topical steroid in childrenORL J Otorhinolaryngol Relat Spec, 71 (2009), pp. 50-55CrossRef (opens in a new tab)Google Scholar (opens in a new tab)[44] (opens in a new tab)D. Rabago, B. Barrett, L. Marchand, R. Maberry, M. Mundt*Qualitative aspects of nasal irrigation use by patients with chronic sinus disease in a multimethod studyAnn Fam Med, 4 (2006), pp. 295-301CrossRef (opens in a new tab)View Record in Scopus (opens in a new tab)Google Scholar (opens in a new tab)[45] (opens in a new tab)J.S. Jeffe, B. Bhushan, J.W. Schroeder Jr.Nasal saline irrigation in children: a study of compliance and toleranceInt J Pediatr Otorhinolaryngol, 76 (2012), pp. 409-413Article (opens in a new tab)Download PDF (opens in a new tab)View Record in Scopus (opens in a new tab)Google Scholar (opens in a new tab)[46] (opens in a new tab)P. Strnad, J. Skoupá, H. Cimrova, P. HorníkEfficacy of hypertonic seawater saline in the treatment of persistent rhinitis/rhinosinusitis*American Society of Pediatric Otolaryngology 2007 Annual Meeting, San Diego, California (2007)Google Scholar (opens in a new tab)[47] (opens in a new tab)M. Friedman, C. Hamilton, C.G. Samuelson, A. Maley, M.N. Wilson, T.K. Venkatesan, * et al.Dead Sea salt irrigations vs saline irrigations with nasal steroids for symptomatic treatment of chronic rhinosinusitis: a randomized, prospective double-blind studyInt Forum Allergy Rhinol, 2 (2012), pp. 252-257CrossRef (opens in a new tab)View Record in Scopus (opens in a new tab)Google Scholar (opens in a new tab)[48] (opens in a new tab)I. Slapak, J. Skoupá, P. Strnad, P. Horník*Efficacy of isotonic nasal wash (seawater) in the treatment and prevention of rhinitis in children*Arch Otolaryngol Head Neck Surg, 134 (2008), pp. 67-74CrossRef (opens in a new tab)View Record in Scopus (opens in a new tab)Google Scholar (opens in a new tab)[49] (opens in a new tab)Y.-H. Wang, C.-P. Yang, M.-S. Ku, H.-L. Sun, K.-H. LueEfficacy of nasal irrigation in the treatment of acute sinusitis in childrenInt J Pediatr Otorhinolaryngol, 73 (2009), pp. 1696-1701Article (opens in a new tab)Download PDF (opens in a new tab)View Record in Scopus (opens in a new tab)Google Scholar (opens in a new tab)[50] (opens in a new tab)M. Ünal, K. Görür, C. ÖzcanRinger-lactate solution versus isotonic saline solution on mucociliary function after nasal septal surgeryJ Laryngol Otol, 115 (2001), pp. 796-797View Record in Scopus (opens in a new tab)Google Scholar (opens in a new tab)[51] (opens in a new tab)D. Pigret, R. JankowskiManagement of post-ethmoidectomy crust formation: randomized single-blind clinical trial comparing pressurized seawater versus antiseptic/mucolytic salineRhinology, 34 (1996), pp. 38-40View Record in Scopus (opens in a new tab)Google Scholar (opens in a new tab)[52] (opens in a new tab)R. Keerl, R. Weber, C. Müller, B. SchickEffectiveness and tolerance of nasal irrigation following paranasal sinus surgeryLaryngorhinootologie, 76 (1997), pp. 137-141CrossRef (opens in a new tab)View Record in Scopus (opens in a new tab)Google Scholar (opens in a new tab)[53] (opens in a new tab)J.M. Pinto, S. Elwany, F.M. Baroody, R.M. NaclerioEffects of saline sprays on symptoms after endoscopic sinus surgeryAm J Rhinol, 20 (2006), pp. 191-196CrossRef (opens in a new tab)View Record in Scopus (opens in a new tab)Google Scholar (opens in a new tab)[54] (opens in a new tab)T. Hofmann, M. Gugatschga, B. Koidl, G. WolfInfluence of preservatives and topical steroids on ciliary beat frequency in vitroArch Otolaryngol Head Neck Surg, 130 (2004), pp. 440-445View Record in Scopus (opens in a new tab)Google Scholar (opens in a new tab)[55] (opens in a new tab)A. Mickenhagen, O. Siefer, P. Neugebauer, E. StennertThe influence of different alpha-sympathomimetic drugs and benzalkoniumchlorid on the ciliary beat frequency of in vitro cultured human nasal mucosa cellsLaryngorhinootologie, 87 (2008), pp. 30-38CrossRef (opens in a new tab)View Record in Scopus (opens in a new tab)Google Scholar (opens in a new tab)